
Measurement Science for Correct Jewelry Fit

Correct jewelry sizing is a healing decision, not only an aesthetic one. This reference covers how piercers measure tissue before an initial piercing, why initial jewelry is longer than the tissue to leave room for swelling (the heal room), why a bar that is too thin is more likely to migrate, typical lengths by site, and when and how to downsize. The percentages and lengths given are studio rules of thumb, not published measurements.
Anthropometry, the measurement of human body dimensions, is rarely taught in body art training. Yet every time a piercer selects initial jewelry, they are making an anthropometric assessment, consciously or not: what are the dimensions of this person's tissue at this site, and what jewelry will accommodate healing without adding mechanical stress? Initial jewelry needs a length or diameter appropriate to the client's anatomy and the placement of the piercing: jewelry that is too small increases the likelihood of swelling, embedding and other complications. Defaulting to one 'standard' size for every client at a given site ignores that.
The basic principle of initial sizing is that the tissue during healing is not the tissue on the day of the procedure. The inflammatory phase of wound healing brings swelling (oedema) that starts within hours and lasts for days [6][11]. Oral tissue swells markedly: swelling is one of the most common problems after tongue piercing [4]. Cartilage swells less, but it is rigid and cannot expand outward, so any constriction from jewelry that is too short does more damage there.
The Heal Room Principle: Why Initial Jewelry Must Be Longer
Initial piercing jewelry must be sized to accommodate peak inflammatory swelling without the jewelry ends pressing into or embedding into the tissue surface. The difference between the resting tissue measurement and the initial jewelry length is the "heal room", the clinical buffer that prevents pressure necrosis during the inflammatory phase.
- »Measurement baseline: Tissue thickness is measured at rest, either by caliper measurement of a gentle tissue pinch, or by marking the entry and exit points of the planned needle pass and measuring the distance between them on the surface. This resting measurement is the minimum internal length required for jewelry that will fit with no swelling.
- »Heal room addition (20-30%): add 20-30% to the resting measurement to set the initial internal length. For a 6 mm resting measurement, initial jewelry of about 7-8 mm; for 8 mm, about 10 mm. These are studio rules of thumb, not published values.
- »Oral piercings, larger buffer: tongue and lip tissue swells more, so piercers add more, typically 40-50% [4]. Initial tongue bars are commonly 16-22 mm, depending on the tongue. Fitting initial jewelry that is too short for an oral piercing is an avoidable error.
- »Embedding risk: when the heal room is too small, the jewelry end (flat disc, ball or bezel) presses into the swollen tissue. Continuous pressure cuts off blood flow locally (pressure ischaemia), and the end can start to sink into the tissue within the first days. Embedding is a known complication of jewelry that is too small. Embedded jewelry needs a piercer or a doctor and often has to be removed, which can end the piercing.
- »Downsizing: once the swelling has gone (typically 2-8 weeks depending on site), the longer initial jewelry is replaced with a shorter, fitted piece. Not downsizing has its own risks: a long post or bar acts as a lever, passing knocks from clothing, teeth and everyday objects to the healing channel. At oral sites, tooth fracture is a common problem after tongue piercing [4].
The Cheese-Cutter Effect: Jewelry That Is Too Thin
The 'cheese-cutter effect' describes migration caused by jewelry whose bar or wire is too thin for the load it carries. The body may treat jewelry that is too thin in gauge like a splinter, resulting in migration or rejection. It is a common mechanical cause of surface piercing failure.
- »Physical mechanism: a thin bar or wire concentrates the load from gravity, movement and pressure on a narrow strip of tissue. The pressure at the tissue-jewelry contact rises, and healing tissue resists it poorly; the jewelry slowly moves through the tissue in the direction of the load, much as a wire cuts through cheese.
- »Surface piercings: the most vulnerable site. A surface bar that is too thin on a flat site such as the abdomen or sternum tends to migrate toward the skin surface and can reject completely over weeks to months. Surface bars are usually 14g (1.6 mm); thinner bars are more likely to migrate, whatever the client prefers for a smaller look.
- »Daith and curved sites: a ring or circular barbell whose inner diameter is too small for the daith applies constant pressure on both ends of the channel. Over weeks this can distort the channel into an oval and push the jewelry toward the free edge of the fold.
- »Septum sizing: the septum "sweet spot", the thin membranous tissue just in front of the septal cartilage, varies in thickness and position between individuals. A small internal diameter that suits one client can press on the tissue of another, which clients describe as the jewelry feeling "too tight." Measuring before choosing the size prevents this.
- »Gauge and contact pressure: pressure is force per unit area. For a bar resting on tissue, the contact area grows with the bar diameter, so a thicker bar spreads the same load more widely. Going from 16g (1.29 mm) to 14g (1.63 mm) lowers contact pressure by about a fifth for the same load. At high-load sites (navel, surface piercings, cartilage), a thicker gauge is a mechanical choice, not only an aesthetic one.
Site-Specific Measurement Protocols
Each piercing site has its own anatomy and needs its own measurement approach. The lengths and timings below are typical studio values for the most common sites, not published standards; measure the individual and adjust.
- »Tongue: With mouth relaxed and tongue in natural position, measure from the planned entry point on the dorsal surface to the planned exit on the ventral surface using sterile calipers or a calibrated probe. Add 50% for initial bar length. Standard initial range: 16–22 mm. Downsize at 4–6 weeks to 14–16 mm.
- »Lip (labret, Monroe, medusa): Measure from the outer lip skin surface to the inner mucosal surface at the planned puncture point. Add 3–4 mm for swelling. Standard initial length: 8–10 mm. Downsize at 4–6 weeks to 6–7 mm flat-back labret. Post length is the most critical variable, a long post leverage against teeth causes enamel wear and gum recession.
- »Nostril: Measure nasal wall thickness at the planned puncture site. Add 2–3 mm. Standard initial: 7–8 mm post. Downsize to 5–6 mm post length at 8–12 weeks. L-bend and nose screw styles should match the nostril wall curvature, a screw too short will not seat correctly and rotate out; too long will protrude into the nasal passage.
- »Navel: Measure vertical tissue depth of the navel shelf with calipers. Tissue depth varies by 4–6 mm between individuals. Standard initial: 10–12 mm vertical internal length with 5 mm top ball, 8 mm bottom ball. Invert navel anatomy requires inverted banana bar. Downsize at 6–10 weeks to fitted length.
- »Helix/flat cartilage: Flat-back labret is the preferred initial jewelry for most flat cartilage sites. Measure tissue thickness including the expected swelling (typically 1–2 mm addition). Standard initial: 8 mm post. Downsize to 6 mm at 3–6 months. Rings should not be used as initial jewelry for cartilage, the ring movement during healing disrupts fistula formation.
- »Septum: Pinch the membranous tissue fold and measure its thickness with calipers. Internal diameter of the ring or retainer must allow 1–2 mm clearance on each side of the tissue fold. Standard: 7–8 mm internal diameter for average anatomy. Larger anatomies require 8–10 mm. Septum retainers (horseshoe style) are sized by internal diameter, not bar length.
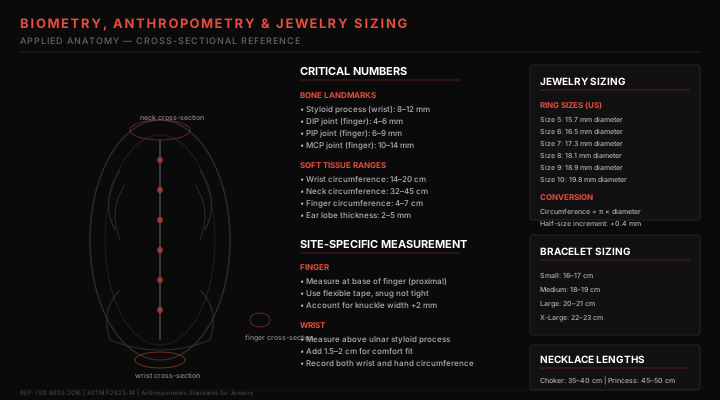
Jewelry Sizing Protocol
Systematic approach to initial jewelry selection, measurement, and the downsize consultation.
- 1Step 1, Tissue measurement before any marking: Measure tissue depth at the planned piercing site before applying stencil or marking pen. Use sterile calipers or a calibrated measurement probe. Document the measurement.
- 2Step 2, Calculate initial jewelry length: apply the heal room rule (about 20-30% for soft tissue, 40-50% for tongue and other oral sites, about 15% for cartilage). Round up to the nearest available size. Document the selected size and the reason.
- 3Step 3, Confirm the gauge for the site: match the gauge to the mechanical load on the site, not to a wish for a smaller look; jewelry that is too thin is more likely to migrate. Surface piercings: usually 14g. Cartilage: 16g or 14g. Soft tissue: 16g-14g; some piercers use 14g or 12g for the septum.
- 4Step 4, Verify all jewelry details before opening the packaging: internal length, gauge, material (implant-grade titanium to ASTM F136 [1] or steel to ASTM F138 / ISO 5832-1 [2] with its certificate, BioFlex® body jewelry or Bioplast), the threading type agreed with the client (internally threaded, threadless or externally threaded), and a smooth, mirror-polished surface free of nicks and scratches. A post and an end bought separately from different suppliers may not have matching threads.
- 5Step 5, Explain the downsize consultation to the client at time of procedure: Tell the client explicitly: "The jewelry I am fitting today is intentionally longer than you will wear long-term. In [site-specific timeframe], you must return for a downsize to the correct fitted length. Keeping the long post is not optional, it causes its own complications." Make this a scheduled follow-up appointment, not a vague recommendation.
- 6Step 6, Downsize consultation assessment: Before removing the initial jewelry, assess: Is the fistula mature enough? (Test: can the jewelry rotate freely with no resistance or bleeding?) Is tissue swelling fully resolved? Is the fistula wall smooth and non-tender? Only proceed with downsize if all three criteria are met.
- 7Step 7, Select downsize jewelry: Measure the fistula channel length at rest. Select jewelry that provides 1–2 mm clearance beyond the fistula on each side (not 20–30%, the heal room buffer is no longer needed post-healing, and a snug fit reduces leverage).
- 8Step 8, Document all jewelry changes: Record: date of original piercing, initial jewelry dimensions, downsize date, downsize jewelry dimensions. This record is clinically valuable if complications arise later and allows consistent follow-up care.

Critical Errors
Sizing errors with clinical and healing consequences.
- Using a single "standard" initial jewelry length for all clients at a given site — This is the most common sizing error. A 10 mm initial labret that fits a client with 7 mm lip depth has 3 mm heal room, acceptable. The same 10 mm post in a client with 5 mm lip depth has 5 mm of excess post, this creates a lever that applies lateral stress to the fresh wound with every lip movement, causing premature scarring and slow healing.
- Prioritising client aesthetic preference over heal room requirements — Clients sometimes request shorter initial jewelry for cosmetic reasons ("I don't want it to stick out so much"). A practitioner who accommodates this request for a fresh oral piercing is prioritising client comfort in the chair over their biological outcome. This is a clinical failure, not a service upgrade.
- Not scheduling a downsize appointment — when downsizing is only mentioned, many clients never come back for it. A long post left in a healed piercing for months becomes a source of chronic irritation and, at oral sites, a risk to the teeth [4].
- Incorrectly measuring tissue depth by compressing tissue with the caliper — Calipers applied with pressure compress soft tissue and underestimate true tissue depth. Measurement should be taken at the minimum pressure needed to achieve tissue contact, the caliper should just touch the surface, not indent it.
- Using rings as initial jewelry for cartilage — a ring moves with every head movement and every touch, which keeps disturbing the healing channel and lengthens healing. Many piercers fit flat-back labrets for initial cartilage jewelry and keep rings for healed cartilage.
- Not accounting for anatomy-specific variation — "Average" measurements from published sources are population averages, the individual in the chair may be 2 standard deviations from average. Practitioners who use published averages instead of measuring the client will oversize some clients and undersize others. Measurement takes 30 seconds. Correcting an embedding takes an appointment and client distress.
- Sizing a client from a previous client — two clients of similar build can have very different septum, navel or lip anatomy. Always measure the individual, even for a repeat piercing at the same site.
Rules and Standards for Body Jewelry
No law or harmonised standard sets dimensions or tolerances for body jewelry. What exists are material and chemical rules, general product safety law, and professional guidance.
- EU Medical Device Regulation (MDR) 2017/745: body jewelry is not a medical device; Annex XVI point 2 covers implants that modify anatomy "with the exception of tattooing products and piercings" [3]. Words such as "implant-grade" or "surgical" describe the material and do not make jewelry a device.
- No harmonised EU standard sets body jewelry dimensions or tolerances; sizes come from manufacturer specifications and professional guidance.
- REACH Annex XVII Entry 27: nickel release of no more than 0.2 μg/cm²/week for post assemblies inserted into pierced parts of the body, and 0.5 μg/cm²/week for other articles in prolonged skin contact [8]. The limits are per unit area, so they apply whatever the gauge.
- General Product Safety Regulation (EU) 2023/988: applies to consumer products, including jewelry, since 13 December 2024; manufacturers must keep technical documentation and the product must be safe [10].
- FDA: body jewelry has no medical purpose and is not regulated as a medical device; no federal standard sets its dimensions.
- Initial jewelry: implant-grade titanium to ASTM F136 [1], steel to ASTM F138 / ISO 5832-1 [2], BioFlex® body jewelry or Bioplast; internally threaded or threadless (the threading type is at the discretion of the piercer and the client), a smooth mirror finish, and a length and gauge appropriate to the client's anatomy.
- ASTM F136 / F138: material specifications for implant-grade titanium alloy and stainless steel; they set composition, not jewelry dimensions.
- FTC Act: claims about jewelry, such as "implant-grade titanium", must be truthful and not misleading.
- Thailand: no dimensional standard for body jewelry was confirmed; studios rely on manufacturer specifications.
- Singapore: body jewelry is not a medical device or health product, so the HSA does not register it; no sizing guideline for piercing practice was confirmed.
- Australia: body art is regulated by the states and territories; no government dimensional standard for body jewelry was confirmed.
Patrick's Note
"I drilled the 20% Rule into every piercer I trained, and I developed it from direct clinical observation, not from a textbook. Early in my piercing career I saw what happened when initial jewelry was sized by how it looked on the day of the piercing. Clients came back in pain 48 hours later with angry, embedded ends. The swelling that looked like 'normal healing' to an untrained eye was actually tissue being compressed by jewelry that had no room to accommodate it. The rule is actually more nuanced than '20%'. For oral piercings, where inflammatory response is always pronounced, I routinely used 40–50% additional length. For cartilage, 15% was typically sufficient. The flat number is a floor, not a ceiling. The practitioner's job is to measure the individual, know the likely swelling response for that site, and apply the appropriate buffer, not to default to a size they have in stock. I also want to be clear about the downsize: this is not optional follow-up care. A long post in a healed piercing is a clinical error that extends over time. Clients who do not return for their downsize develop leverage trauma, gum recession, tooth chipping, and hypertrophic scarring from chronic mechanical irritation. The appointment needs to be booked at the time of the original procedure. Not suggested. Booked."
Founder & Piercing Expert
Poli International
Common Questions
▸What is anthropometry in the context of professional piercing and why is it important for practitioners to understand this measurement science?
▸Which working numbers should a piercer apply when selecting initial jewelry, and where do they come from?
▸What is the clinical protocol for performing initial jewelry sizing and the subsequent mandatory downsize procedure for a healing piercing?
▸How does insufficient jewelry length contribute to focal pressure ischemia or embedding, and what specific buffer rules mitigate these common complications?
▸What mechanical forces cause the cheese-cutter effect, and how can a practitioner prevent migration through jewelry gauge and diameter selection?
▸Which regulations and standards apply to body jewelry sizes and materials?
Anatomical Plates
Free Body Art Wall Posters
Print-ready reference posters for your studio or your own wall. Free to download and display, embed on your own site with attribution. Click any poster to preview it full size before downloading.
Page map · Biometry, Anthropometry & Jewelry Sizing
- Biometry, Anthropometry & Jewelry Sizing
- Critical Numbers
- Heal room
- Typical initial labret/flat back length
- Gauge and migration
- The Heal Room Principle
- Measurement baseline
- Heal room addition (20-30%)
- Oral piercings
- The Cheese-Cutter Effect
- Physical mechanism
- Surface piercings
- Daith and curved sites
- Site-Specific Measurement Protocols
- Tongue
- Lip (labret, Monroe
- Nostril
- Jewelry Sizing Protocol
- Step 1, Tissue measurement before any marking
- Step 2, Calculate initial jewelry length
- Step 3, Confirm the gauge for the site
- Critical Errors
- Using a single "standard" initial jewelry length for all clients at a given site
- Prioritising client aesthetic preference over heal room requirements
- Not scheduling a downsize appointment
- Rules and Standards for Body Jewelry
- European Union
- United States
- ASEAN & Asia-Pacific
- Patrick's Note
- Related Topics
- Anatomical Geometry, Kinetic Anatomy
- Wound Healing Biology
- Metallic Biocompatibility
Built from this page's own sections, so it always matches what is below. It is a map of the page, not a set of claims, and carries no citations of its own.
Technical Specifications
| Parameter | Standard / Value |
|---|---|
| Heal Room Buffer, Soft Tissue | 20–30% of resting tissue measurement |
| Heal Room Buffer, Oral Sites | 40–50% of resting tissue measurement |
| Heal Room Buffer, Cartilage | About 15-20% of resting tissue measurement |
| Initial Jewelry Materials | Titanium ASTM F136 [1]; steel ASTM F138 / ISO 5832-1 [2]; BioFlex® body jewelry; Bioplast |
| Initial Labret Length (lip) | 8–10 mm typical |
| Healed Labret Length (lip) | 6–7 mm typical |
| Initial Tongue Bar Length | 16–22 mm (anatomy-dependent) |
| Healed Tongue Bar Length | 14–16 mm typical |
| Initial Nostril Post Length | 7–8 mm |
| Healed Nostril Post Length | 5–6 mm |
| Initial Navel Bar Length | 10–12 mm vertical |
| Healed Navel Bar Length | 8–10 mm vertical |
| Contact Pressure, 16g to 14g | About a fifth lower for the same load |
| Usual Surface Piercing Gauge | 14g (1.6 mm); thinner bars migrate more readily |
Revision Deck
14 cards, taken directly from this page's specifications. Nothing here is generated: the deck is the same reviewed data as the table above. See the full table.
Printable wall chart (A4) — the critical numbers, the do-nots and the applicable standards on one page for the bench.
References
- [1]ASTM F136: Standard Specification for Wrought Titanium-6Aluminum-4Vanadium ELI (Extra Low Interstitial) Alloy for Surgical Implant Applications (UNS R56401).https://store.astm.org/f0136-13r21e01.html
- [2]ASTM F138: Standard Specification for Wrought 18Chromium-14Nickel-2.5Molybdenum Stainless Steel Bar and Wire for Surgical Implants (UNS S31673).https://store.astm.org/f0138-19.html
- [3]Regulation (EU) 2017/745 on medical devices (MDR), Annex XVI point 2.https://eur-lex.europa.eu/eli/reg/2017/745/oj
- [4]Meltzer D.I. (2005) "Complications of body piercing." American Family Physician 72(10):2029–2034.https://www.aafp.org/pubs/afp/issues/2005/1115/p2029.html
- [5]Angel E. (2009) The Piercing Bible: The Definitive Guide to Safe Body Piercing. Crossing Press. ISBN 978-1-58091-193-3.https://www.piercingbible.com/the-piercing-bible-book
- [6]Eming S.A., Martin P., Tomic-Canic M. (2014) "Wound repair and regeneration: mechanisms, signaling, and translation." Science Translational Medicine 6(265):265sr6.https://doi.org/10.1126/scitranslmed.3009337
- [7]Stirn A., Hinz A., Brähler E. (2006) "Prevalence of tattooing and body piercing in Germany and perception of health, mental disorders, and sensation seeking among tattooed and body-pierced individuals." Journal of Psychosomatic Research 60(5):531-534.https://doi.org/10.1016/j.jpsychores.2005.09.002
- [8]Regulation (EC) No 1907/2006 (REACH), Annex XVII, Entry 27 (nickel).https://echa.europa.eu/substances-restricted-under-reach
- [9]Gray's Anatomy: The Anatomical Basis of Clinical Practice, 42nd ed. (2020). Standring S. (ed). Elsevier.https://shop.elsevier.com/books/grays-anatomy/standring/978-0-7020-7705-0
- [10]Regulation (EU) 2023/988 on general product safety (GPSR).https://eur-lex.europa.eu/eli/reg/2023/988/oj
- [11]Rodrigues M. et al. (2019) "Wound healing: a cellular perspective." Physiological Reviews 99(1):665–706.https://doi.org/10.1152/physrev.00067.2017
Put Science Into Practice
This technical standard is the architectural foundation for our professional analytical tools.