

Needle Taper, Apex, and Gauge Engineering

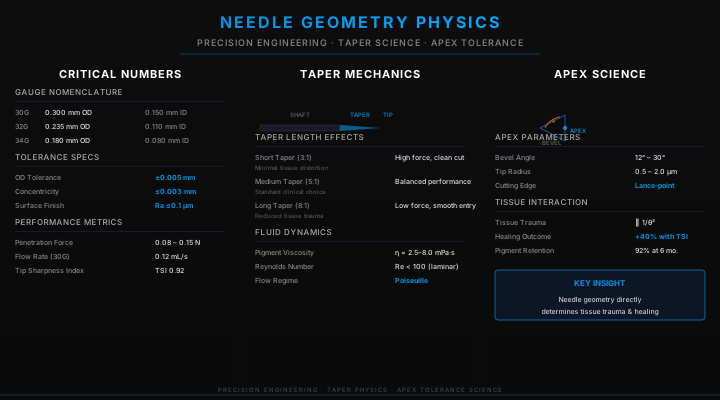
Needle geometry directly determines tissue trauma, healing outcome, and pigment retention. This reference covers taper physics, apex tolerance science, gauge nomenclature, fluid dynamics of pigment delivery, correct needle selection protocols, and the manufacturing standards that separate professional instruments from substandard alternatives.
A needle used in body art is not a simple sharp object, it is a precision fluid-delivery system whose geometry is engineered to three simultaneous goals: minimise tissue displacement at penetration, create the correct channel diameter for the intended jewelry gauge or pigment deposition, and wick fluid (ink or anaesthetic) reliably from reservoir to wound bed. Every millimetre of taper length, every tenth of a micrometer of apex radius, and every increment of gauge directly affects tissue trauma, bleeding, and long-term healing. Practitioners who treat needle selection as interchangeable are making the same mistake as a surgeon choosing a scalpel by price.
The geometry of a needle tip operates through two physical mechanisms: cutting and displacement. A correctly engineered apex with a fine radius (< 12 μm) and a long taper (> 4.5 mm) cuts tissue fibres with minimal lateral displacement, the needle passes through like a wedge splitting grain along the fibre. A blunt apex or steep short taper instead compresses and tears tissue ahead of the needle tip, damaging more tissue than a fine-taper needle of the same gauge. This distinction is invisible to the naked eye but measurable in healing time and client comfort.
Taper Mechanics: What the Length Actually Does
The taper is the tapered section between the needle body and the apex. Its length determines the angle at which the needle engages tissue, and therefore the ratio of cutting force to lateral compression force during penetration.
- »Short taper (ST): 1.5–2.5 mm. Steep angle (6°–10°). High lateral displacement force. Rapid pigment deposition per pass due to large channel diameter relative to penetration depth. Used for solid colour packing where saturation speed matters more than precision.
- »Medium taper (MT/RT, "regular"): 3.0–4.0 mm. Balanced between displacement and fluid channel. Workhorse configuration for general lining and shading.
- »Long taper (LT): 4.5–5.5 mm. Taper angle 2.5°–3.5°. Minimal lateral displacement, smooth tissue entry, lower trauma per pass. Preferred for detail work, fine lines, portraiture, and sensitive anatomical locations.
- »Extra-long taper (ELT/HLT): 6.0–7.0 mm. Near-surgical cutting geometry. Designed for single-pass work on challenging skin textures (scar tissue, heavily sun-damaged dermis). Risk of ink fallout if machine speed is not matched to fluid wicking rate.
- »Bugpin configurations: Refers to a thinner needle wire (0.30 or 0.25 mm, 0.20 mm for "super" bugpins, vs. the standard 0.35 mm), not taper length. Bugpin + long taper = maximum precision, minimum trauma. Used almost exclusively for fine-line realism and cosmetic tattooing.
Apex Science: The Physics of the Tip
The apex is where all penetration physics converges. Its sharpness is defined by the radius of curvature measured at the needle point under scanning electron microscopy (SEM). Penetration force rises with apex radius: a blunter point spreads the same push over a larger contact area, so it compresses more tissue before the skin gives way.
- »Professional-grade apex: < 12 μm radius. No published penetration-force figure exists for body art needles; the force depends on the needle, the skin and the body site.
- »Consumer-grade apex: 15–30 μm. Perceivable as "scratchy" entry. Requires higher machine voltage or hand pressure to achieve same penetration depth, amplifying lateral micro-tears.
- »Substandard/damaged apex: > 30 μm. Visible deformation under 10× loupe. Must never be used, once a needle has contacted any hard surface (tray, vial cap, bone) it is compromised regardless of sterility status.
- »Apex asymmetry: Manufacturing defects or post-production damage can create a beveled or hooked apex. This creates directional tissue tearing, the needle path curves inside tissue, producing ragged wound edges that heal with irregular pigment borders.
- »Surface finish at the apex: Even a geometrically sharp apex with high Ra (> 0.2 μm) surface roughness will shred collagen fibres. Electrolytic polishing (standard in professional needles) reduces Ra to < 0.08 μm and removes microburs from the grinding process.
Gauge Nomenclature and Fluid Dynamics
Body art uses two different numbering systems: tattoo needles are numbered by wire diameter (#12 = 0.35 mm, #10 = 0.30 mm, #8 = 0.25 mm), while piercing needles are hollow and named for the jewelry gauge they pass (12g, 14g, 16g...), where a larger number means a narrower needle. Understanding the fluid dynamics of pigment wicking is essential for correct machine configuration.
- »Wire gauge to diameter: 12g = 2.05 mm OD, 14g = 1.63 mm, 16g = 1.29 mm, 18g = 1.02 mm, 20g = 0.81 mm, 23g = 0.57 mm. Each gauge step = approximately 20% reduction in cross-sectional area.
- »Hollow needle internal volume: Piercing needle internal diameter is typically 60–70% of outer diameter. A 14g needle with 0.3 mm wall has ~1.03 mm ID and an internal volume of ~0.83 mm²/mm, sufficient for a single rapid ink column delivery.
- »Capillary wicking (tattoo): Tattoo needle groupings (3RL, 7M, etc.) rely on capillary action between adjacent wires to wick ink. Tighter groupings (smaller inter-wire spacing) produce slower but more controlled ink flow. This is why a 7-needle round liner deposits pigment differently than a 7-needle magnum despite the same needle count.
- »Viscosity matching: High-viscosity inks (> 2,000 cP) resist capillary wicking, machines must run slower to allow ink column refill between strokes. Low-viscosity inks (< 300 cP) over-saturate, increasing blowout risk in thin or compromised dermis.
- »Needle depth and dermis targeting: Pigment must reach the upper-to-mid dermis, below the epidermis. How deep that is depends on the body site: the dermis is under 1 mm thick on the inner wrist and several millimetres thick on the back. Too shallow: epidermis-only deposition, ink exfoliates within weeks. Too deep: subcutaneous fat entry, ink migrates laterally, producing "blowout" diffusion.
Needle Selection and Handling Protocol
Systematic approach to needle selection, pre-procedure inspection, and safe handling, from packaging to sharps disposal.
- 1Step 1, Match gauge to procedure: piercing gauge must match intended jewelry internal diameter exactly (14g needle for 14g threadless or internally threaded jewelry). Mismatch creates either channel collapse (under-gauge) or excess tissue death (over-gauge).
- 2Step 2, Match taper to technique: detail line work → long taper (LT or ELT); solid colour pack → short-to-medium taper; portrait realism on challenging skin → extra-long taper or bugpin configuration.
- 3Step 3, Inspect packaging before opening: check that the sterilisation indicator has changed colour as the manufacturer's key shows (EO and steam indicators use different colours). Reject any damaged, discoloured, or previously-opened packaging.
- 4Step 4, Examine needle tip under loupe (10×) before every procedure: apex must show a single clean point with no visible asymmetry, hooks, or burrs. Any deformity = discard.
- 5Step 5, Handle needles by the body only, never touch the taper or apex with fingers, gloves, or instruments. A single contact with any hard surface invalidates the apex.
- 6Step 6, For tattoo: verify cartridge or needle bar lockup is secure before test run. A loose needle bar produces irregular depth variation and micro-vibration that increases lateral tissue damage.
- 7Step 7, For piercing: pre-load jewelry onto needle tail (cork method or receiving tube) before penetration, so jewelry follows needle through channel in a single pass. Never make a second pass to "find" the channel.
- 8Step 8, Machine speed and depth calibration: run the machine on practice skin before each session to verify consistent depth and ink flow, never on your own thumb or hand. Adjust voltage/speed in 0.5V increments until needle entry is smooth with minimal surface drag.
- 9Step 9, During procedure: monitor needle path angle, maintain consistent entry angle relative to skin surface. Angular deviation > 5° from perpendicular (or planned bevel angle for piercing) produces asymmetric tissue channels.
- 10Step 10, Immediate post-use: do not recap. Drop the used needle or cartridge straight into a puncture-resistant sharps container within reach. If recapping truly cannot be avoided, use the one-hand scoop method, never two hands. Never set a used needle down on the tray between clients.
- 11Step 11, Cartridge/needle disposal: dispose as regulated medical sharps waste per OSHA 29 CFR 1910.1030 (USA) or your national clinical-waste rules. Never disassemble cartridges, dispose whole.
- 12Step 12, Document any needlestick injury immediately: flush with water (do not squeeze), report to supervisor, initiate post-exposure protocol per facility policy.
? Open question, not established
Do long tapers really heal faster?
Long-taper needles are widely held to displace less tissue, reduce trauma and speed healing, and that belief drives a great deal of needle selection. The mechanical argument is plausible: a shallower taper angle should distribute penetration force over a longer distance. What is missing is evidence that the effect survives contact with the other variables that dominate a real procedure, above all depth, speed, and the number of passes over the same skin.
Held by: Needle and machine manufacturers in their product documentation, and practitioner consensus. This is the trade working assumption.
What would settle it: A controlled comparison of taper geometry at matched depth, speed and pass count, measuring healing time or histological trauma rather than artist preference. No such study was found.

Critical Errors
Engineering and procedural errors in needle selection and handling with documented consequences.
- Using short-taper needles for fine-line detail work — excessive lateral tissue displacement widens the line edge beyond the intended boundary. Results in "blown" lines that appear correct immediately post-procedure but spread during healing.
- Ignoring gauge-to-jewelry mismatch for piercing — even a half-gauge deviation (e.g., 14g needle with 16g jewelry) creates a loose channel. Loose channels do not heal snugly around jewelry, they form a fluid-filled corridor that dramatically increases migration and rejection rates.
- Running high-viscosity ink at high speed — capillary wicking cannot keep up with needle stroke frequency, creating a dry pass that tears dermis without depositing pigment. Practitioners mistake this for "not enough voltage" and increase speed, worsening the problem.
- Touching the needle tip, even with a gloved finger — the contact can bend or burr a fine apex, and it breaks the sterile field. A needle that feels "fine" can still be compromised; treat any contact with the tip as a reason to discard it.
- Reusing a needle for a second client even with re-sterilization attempt — heat sterilization does not restore apex geometry damaged by first use, it only addresses sterility. A used-and-resterilized needle has the same blunt apex and collagen-shredding roughness as before sterilization.
- Tattooing into dermis based on voltage alone without depth calibration — voltage sets how fast the needle runs (and, on coil machines, how hard it hits), not how deep it goes; depth comes from the stroke, the needle reach and the artist's hand. Dermis thickness varies about fourfold by body site (inner wrist: ~0.9 mm; back: ~3.5 mm). Setting up by voltage alone is guesswork.
- Disposing of needles in general waste — breaks OSHA rules in the USA and clinical-waste rules in most countries. Creates sharps injury risk for waste handlers, and can lead to fines or prosecution.
- Using needles beyond labelled expiry date — EO sterilization efficacy is validated to a fixed shelf life (typically 5 years from manufacture). Packaging permeability increases with time. Expired needles may remain sterile in practice but the manufacturer's sterility guarantee is void.
Manufacturing & Safety Standards
Key standards governing needle design, sterility, and clinical use across major regulatory jurisdictions.
- EU MDR 2017/745: Medical Devices Regulation. Tattoo and piercing needles are not medical devices under it (Annex XVI expressly excludes products for tattooing); it covers only needles sold as hypodermic medical devices
- EN ISO 7864: Sterile hypodermic needles, dimensional and performance requirements [1]
- ISO 10993 (series): Biological evaluation of medical devices, material biocompatibility
- EU Directive 2010/32/EU: Prevention of sharps injuries in the hospital and healthcare sector; studios are bound only where national law extends it, but its rules are good practice
- EN ISO 11135: EO sterilization process validation and routine control (replaced the withdrawn EN 550)
- FDA 21 CFR 880.5570: Hypodermic single lumen needle, a Class II medical device; it covers needles sold as medical devices, not tattoo needles
- ASTM F2132: puncture resistance of sharps DISPOSAL CONTAINERS, not a body piercing needle standard [2]; no ASTM specification specific to body art needles was identified (checked 2026-08-02)
- OSHA 29 CFR 1910.1030: Bloodborne Pathogens Standard, sharps handling, disposal, and exposure control
- ISO 7864: Sterility and dimensional requirements for hypodermic needles, the usual reference for hollow piercing needles; it does not cover tattoo needles [1]
- State-level body art regulations: Most states require single-use sterile needles; some specify ISO or ASTM compliance
- Thailand: No dedicated needle standard; practice follows ISO 7864 by industry convention [1]; disposal governed by Infectious Waste Regulations B.E. 2545
- Australia (comparator): tattoo and piercing needles are not regulated as medical devices by the TGA; state skin-penetration rules require sterile single-use needles; ISO 7864 is the reference [1]; Safe Work Australia sharps guidance
- Singapore: HSA Medical Device classification, hypodermic needles require product registration; disposal under NEA Scheduled Waste regulations
- Philippines: FDA registration required for needles sold as medical devices; disposal under RA 6969 (Toxic Substances and Hazardous and Nuclear Wastes Control Act)
- Industry expectation (all ASEAN): ISO 7864 compliance and CE marking are treated as quality proxies in the absence of domestic equivalents [1]
Patrick's Note
"I have been on both sides of this, as a practitioner and as a manufacturer supplying studios across Europe. The single biggest quality gap I observed was not in sterilization protocols or aftercare advice: it was in needle grade. Studios would invest in expensive machines, premium inks, and high-end jewelry, then order the cheapest needles available to 'save money'. A precision tattoo machine driving a substandard needle is like a Formula 1 car on flat tyres. All that engineering advantage disappears at the point where metal meets skin. When I moved into manufacturing BioFlex® components, the same principle applied: surface finish tolerances that seem academic on paper, Ra < 0.1 μm, dimensional tolerances of ±0.02 mm, are directly visible in clinical outcomes. They show up in healing times, in rejection rates, in whether a piercing settles cleanly or migrates. Good geometry is not a luxury for discerning clients. It is the baseline standard that defines the profession. See also: [Metallic Biocompatibility](/wiki/metallic-biocompatibility/) for how surface finish on metal jewelry parallels needle apex science."
Founder & Piercing Expert
Poli International
Common Questions
▸What is needle geometry and why does it matter to a working professional?
▸What are the key engineering numbers and thresholds for professional-grade needles?
▸How is the correct procedure for needle selection and handling carried out?
▸What happens when using short-taper needles for fine-line work and how is this avoided?
▸What is the consequence of a gauge-to-jewelry mismatch in piercing and how is it prevented?
▸What do the current regulations and manufacturing standards require for needles?
Anatomical Plates
Free Body Art Wall Posters
Print-ready reference posters for your studio or your own wall. Free to download and display, embed on your own site with attribution. Click any poster to preview it full size before downloading.
Page map · Needle Tip Geometry & Blunt Tip Physics Explained
- Needle Tip Geometry & Blunt Tip Physics Explained
- Critical Numbers
- Standard taper range
- Apex radius tolerance
- Taper Mechanics
- Short taper (ST)
- Medium taper (MT/RT, "regular")
- Apex Science
- Professional-grade apex
- Consumer-grade apex
- Gauge Nomenclature and Fluid Dynamics
- Wire gauge to diameter
- Hollow needle internal volume
- Needle Selection and Handling Protocol
- Step 1, Match gauge to procedure
- Step 2, Match taper to technique
- Do long tapers really heal faster?
- Critical Errors
- Using short-taper needles for fine-line detail work
- Ignoring gauge-to-jewelry mismatch for piercing
- Manufacturing & Safety Standards
- European Union
- United States
- Patrick's Note
- Related Topics
- Metallic Biocompatibility
- Infection Control, Bloodborne Pathogens
Built from this page's own sections, so it always matches what is below. It is a map of the page, not a set of claims, and carries no citations of its own.
Technical Specifications
| Parameter | Standard / Value |
|---|---|
| Standard Taper Range | 1.5 mm (ST) – 7.0 mm (ELT) |
| Apex Radius, Professional Grade | < 12 μm |
| Apex Radius, Substandard | > 25 μm |
| Surface Roughness (Ra) | < 0.1 μm (electrolytic polish) |
| Taper Angle, Long Taper | 2.5°–3.5° |
| Taper Angle, Short Taper | 6°–10° |
| Dimensional Tolerance | ± 0.02 mm |
| Standard Piercing Gauges | 12g (2.05 mm) – 23g (0.57 mm) |
| Wall Thickness, 14g Piercing Needle | 0.30–0.35 mm |
| Optimal Ink Viscosity Range | 500–2,000 cP |
| Target Depth | Upper-to-mid dermis (depth varies by body site) |
| Penetration Force | No published figure for body art needles |
| Sterilization Method | EO (ethylene oxide) or gamma, SAL 10⁻⁶ |
| Shelf Life (EO sterile) | 5 years from manufacture date |
| Wire Diameter, Bugpin | 0.30 or 0.25 mm (0.20 mm super bugpin) vs. standard 0.35 mm |
Revision Deck
15 cards, taken directly from this page's specifications. Nothing here is generated: the deck is the same reviewed data as the table above. See the full table.
Printable wall chart (A4) — the critical numbers, the do-nots and the applicable standards on one page for the bench.
References
- [1]ISO 7864:2016, Sterile hypodermic needles for single use, requirements and test methods.https://www.iso.org/standard/63822.html
- [2]ASTM F2132-01, Standard Specification for Puncture Resistance of Materials Used in Containers for Discarded Medical Needles and Other Sharps.https://www.astm.org/f2132-01.html
- [3]EU Medical Devices Regulation 2017/745.https://eur-lex.europa.eu/legal-content/EN/TXT/?uri=CELEX%3A32017R0745
- [4]ISO 10993-1:2018, Biological evaluation of medical devices, evaluation and testing.https://www.iso.org/standard/68936.html
- [5]Grice E.A., Segre J.A. (2011) "The skin microbiome." Nature Reviews Microbiology 9(4):244–253.https://doi.org/10.1038/nrmicro2537
- [6]OSHA 29 CFR 1910.1030, Bloodborne Pathogens Standard.https://www.osha.gov/laws-regs/regulations/standardnumber/1910/1910.1030
- [7]EU Directive 2010/32/EU on prevention of sharps injuries in the hospital and healthcare sector.https://eur-lex.europa.eu/legal-content/EN/TXT/?uri=CELEX%3A32010L0032
- [8]Association of Professional Piercers, Piercing Resource Guide (current ed.): Needle Specifications.https://safepiercing.org/publications/
- [9]Kluger N. (2016) "Cutaneous and systemic complications associated with tattooing." La Presse Medicale 45(6-7):567-576.https://doi.org/10.1016/j.lpm.2016.02.016
- [10]Jushiddi M.G. et al. (2020) "Bevel angle study of flexible hollow needle insertion into biological mimetic soft-gel: simulation and experimental validation." Journal of the Mechanical Behavior of Biomedical Materials 111:103896.https://doi.org/10.1016/j.jmbbm.2020.103896
Put Science Into Practice
This technical standard is the architectural foundation for our professional analytical tools.