
Topical anaesthetics promise painless tattooing. They also carry methemoglobinemia risk, can change skin texture and ink absorption, and now face regulatory restrictions in multiple jurisdictions. Here is what the evidence says, what a studio protocol needs to cover, and how the regulatory landscape is shifting.
A client arrives with a tube of numbing cream they bought online, already applied, asking if you can tattoo over it. Or they message you the week before: "Should I get numbing cream for my session?"
The instinct to say yes is understandable. Less client movement, fewer breaks, a smoother session. But topical anaesthetics for tattooing sit in a grey zone where pharmacology, broken-skin absorption, and regulation intersect, and the risks are not widely understood even among experienced artists.
This article covers what is in these creams, how they work on intact versus broken skin, the systemic toxicity risks that matter in a studio setting, the rapid regulatory shift (Oregon banned artist-applied numbing in April 2026, and other US states are watching), and what a safe protocol looks like if you do allow them.
What is in numbing cream: the active ingredients
Most over-the-counter and compounded topical anaesthetics for tattooing contain one or more of these four active ingredients. All are amide-type local anaesthetics that block voltage-gated sodium channels in peripheral nerves, preventing action potential propagation and the sensation of pain.
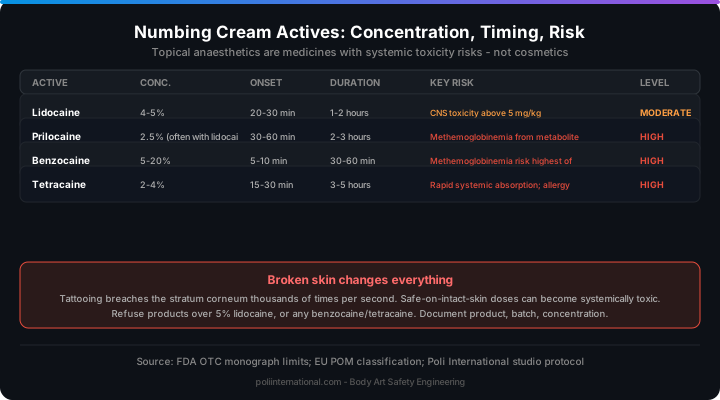
| Ingredient | Typical OTC strength | Onset | Duration | Key risk |
|---|---|---|---|---|
| Lidocaine | 4-5% | 20-30 min | 1-2 hours | CNS toxicity above 5 mg/kg systemic dose 🔶 MODERATE |
| Prilocaine | 2.5% (often with lidocaine as EMLA) | 30-60 min | 2-3 hours | Methemoglobinemia from o-toluidine metabolite 🔴 HIGH |
| Benzocaine | 5-20% | 5-10 min | 30-60 min | Methemoglobinemia risk highest of all topical anaesthetics 🔴 HIGH |
| Tetracaine | 2-4% | 15-30 min | 3-5 hours | Rapid systemic absorption; ester-type higher allergy risk 🔴 HIGH |
Prilocaine and benzocaine are the two worth singling out for studio awareness. Both carry a specific and potentially fatal adverse effect called methemoglobinemia: the drug metabolite oxidises the iron in haemoglobin from Fe²⁺ to Fe³⁺, creating methaemoglobin that cannot carry oxygen. The result is functional anaemia. Cyanosis (blue-grey skin, especially lips and nail beds) appears when methaemoglobin exceeds 10-15%. At levels above 30-40%, the patient becomes lethargic, dyspnoeic, and may lose consciousness. At levels above 70%, it is fatal without methylene blue treatment. The FDA has flagged benzocaine-associated methemoglobinemia in over-the-counter products repeatedly since 2006.
Broken skin changes everything: why tattooing over numbing cream is different from intact-skin application
Topical anaesthetics are designed and tested for application to intact skin. The stratum corneum, the outermost layer of the epidermis, functions as a lipid barrier that slows drug penetration. Most numbing creams instruct users to apply a thick layer under an occlusive dressing for 30 to 60 minutes before a procedure to overcome this barrier.
Tattooing breaks that barrier. The needle punctures the epidermis at 50 to 3,000 times per second, creating thousands of microchannels directly into the dermis. If numbing cream residue is still present on the skin surface when the needle enters, two things happen:
1. Accelerated systemic absorption. The anaesthetic bypasses the stratum corneum and enters dermal capillaries directly. Doses that are safe on intact skin can become systemically toxic when the barrier is removed. Lidocaine toxicity is dose-dependent: plasma concentrations above 5 µg/mL produce CNS symptoms (lightheadedness, tinnitus, perioral numbness, metallic taste), and concentrations above 10 µg/mL can cause seizures and cardiovascular collapse.
2. Unknown ink interaction. Topical anaesthetics change skin chemistry. Most are formulated in lipophilic bases (petrolatum, mineral oil, or PEG) that leave a residue on the skin surface. That residue can mix with tattoo ink in the dermis. No published study has systematically examined whether lidocaine or prilocaine in the dermal microenvironment alters pigment particle dispersion, phagocytosis by dermal macrophages, or long-term ink retention. The interaction is simply unknown.
Some artists report that numbed skin "takes ink differently", that the colour looks muted when healed or that lines are harder to read because the tissue is wetter or softer than expected. These observations are anecdotal, but they align with what is known about how local anaesthetics cause vasodilation (lidocaine is a vasodilator at clinical concentrations, which is why epinephrine is often added to counteract it). Increased local blood flow could increase ink washout during the procedure.
The regulatory landscape: Oregon, FDA, and EU
In April 2026, the Oregon Health Authority issued a ruling that made Oregon the first US state to explicitly prohibit tattoo artists from applying topical numbing products to clients. The ruling interprets anaesthetic application by a non-licensed individual as the unlicensed practice of medicine. Clients may still apply their own numbing cream before arriving, but the artist cannot supply it, apply it, or instruct the client on its use during the session. The penalty structure includes fines and potential licence suspension.
The Oregon move is significant because it sets a precedent other state boards are watching. California, New York, and Texas have not yet issued equivalent rulings as of mid-2026, but the Oregon language provides a template. The core legal argument is straightforward: topical anaesthetics are medicines with known systemic risks. Applying them to a client's skin before a procedure that breaks that skin constitutes drug administration. Tattoo licences authorise body art, not pharmacology.
FDA position
The FDA does not regulate tattoo ink or tattooing procedures directly, leaving that to state and local authorities. However, it does regulate topical anaesthetics as over-the-counter drug products. The agency has issued multiple safety communications about compounded topical anaesthetics, particularly high-concentration lidocaine products (10%, 20%, 30%) sold online without prescription. These "compounded" creams often contain lidocaine concentrations far above the 4-5% OTC monograph limit and have been associated with seizures, cardiac arrhythmias, and deaths, predominantly in cosmetic procedure settings where large body-surface areas were covered under occlusion.
EU classification
In the EU, lidocaine and prilocaine are classified as prescription-only medicines (POM). Over-the-counter availability varies by member state; some allow low-concentration lidocaine creams (up to 5%) as pharmacy-only medicines, while others require a prescription for any concentration. The EU Cosmetics Regulation (EC 1223/2009) does not apply to products making anaesthetic claims, which fall under medicinal product regulation (Directive 2001/83/EC). A numbing cream marketed as a tattoo accessory in the EU is almost certainly misclassified if it is not registered as a medicinal product.
What a safe numbing cream protocol looks like (if your jurisdiction allows it)
If you practise in a jurisdiction where artist-applied numbing cream remains legal, and you choose to permit clients to use it, these steps reduce the risks that are within your control:
1. Client applies their own. Do not supply the cream, do not apply it, and do not instruct on application technique beyond "follow the manufacturer's instructions." This mirrors the Oregon rule even in states where it is not yet law, because it moves the liability to the client and the manufacturer.
2. Know the concentration. Ask to see the tube. If the lidocaine concentration exceeds 5%, or if the product contains benzocaine or tetracaine, refuse to tattoo over it. Document the product name, batch number, and concentration in the client's consent form.
3. Wipe it off completely before starting. Numbing cream should be removed with a clean, damp cloth after the recommended contact time and before the skin is prepared for tattooing. The goal is to avoid driving residual cream into the dermis with the needle. Wipe, then perform your standard skin prep (alcohol, chlorhexidine, or the antiseptic your studio protocol uses).
4. Limit the treated surface area. Systemic absorption scales with the area covered. A full back covered in 5% lidocaine cream under occlusion for an hour exposes the client to a much higher systemic dose than a small wrist piece. There is no published safe-area limit for tattooing specifically, but the FDA warning about compounded creams notes that covering large areas under occlusion increases risk substantially.
5. Watch for CNS symptoms. Lightheadedness, ringing in the ears (tinnitus), a metallic taste, perioral numbness or tingling that was not present before the cream was applied, these are early signs of lidocaine systemic toxicity. Stop the session. If symptoms progress (slurred speech, drowsiness, muscle twitching), call emergency services.
6. Document everything. Consent form entries: product name, active ingredient and concentration, time of application, time of removal, area covered, whether occlusion was used, and a signed statement that the client applied the product themselves. If something goes wrong, this documentation is the difference between a defendable incident and an indefensible one.
Alternatives to numbing cream that are evidence-supported
Several non-pharmacological pain management strategies have better safety profiles and reasonable evidence for procedural pain:
| Method | Mechanism | Evidence level | Practical for tattooing? |
|---|---|---|---|
| Ice / cold packs | Slows nerve conduction velocity; vasoconstriction reduces bleeding | Well-established for acute procedural pain; short duration | Yes, for breaks during the session. Not before, as vasoconstriction may affect stencil transfer |
| Vibration anaesthesia | Gate control theory: non-painful mechanical stimulus closes the "gate" to pain signals in the dorsal horn | Moderate; supported by dental procedure and injection-pain studies | Limited for large areas; vibration devices can interfere with needle precision |
| Distraction techniques | Attentional modulation of pain perception; reduces pain by occupying cognitive bandwidth | Strong for mild-to-moderate pain; weak for high-intensity procedural pain | Highly practical: music, conversation, visual focus points |
| Breathing techniques | Slow, controlled exhalation during needle contact reduces sympathetic nervous system activation | Moderate; supported by labour pain and procedural anxiety literature | Highly practical; zero cost, zero risk |
| Session pacing | Shorter sessions with breaks prevent pain summation and central sensitisation | Clinical consensus | Standard practice; limits single-session coverage |
None of these eliminate pain the way 5% lidocaine does. But they also carry zero risk of methaemoglobinemia, CNS toxicity, or regulatory violation. For clients who genuinely cannot tolerate a session without pharmacological numbing, the correct answer in most jurisdictions is to refer them to a medical professional who can administer local anaesthetic injections under appropriate supervision, not to reach for a tube of cream the client bought online.
Key takeaways
- Numbing creams are medicines with systemic toxicity risks, not cosmetic products. Lidocaine, prilocaine, benzocaine, and tetracaine all have established adverse-effect profiles that become more dangerous when applied to skin that will be broken by needles.
- Broken skin means accelerated absorption. The safe dose on intact skin does not predict the safe dose when the stratum corneum is breached thousands of times per second during tattooing.
- Methemoglobinemia from prilocaine or benzocaine is rare but potentially fatal, and presents silently: a client turns blue-grey, not red or swollen. If your studio cannot recognise early cyanosis, you should not allow products containing these ingredients.
- Oregon banned artist-applied numbing in April 2026. Other US states are likely to follow. The regulatory direction is clear: numbing cream application is drug administration, and tattoo licences do not authorise it.
- Document everything, and let the client apply their own cream if your jurisdiction still permits it. A consent form entry with product name, batch, concentration, and a signed self-application statement is the minimum defensible standard.
- Cold, vibration, breathing, and pacing are safer alternatives. They do not eliminate pain, but they carry zero systemic risk and zero regulatory exposure.
Frequently asked questions
Q: Does numbing cream affect how tattoo ink heals?
The direct answer: there is no published study on numbing cream residue in the dermis and its effect on ink retention. The indirect answer: lidocaine is a vasodilator, meaning it increases local blood flow. More blood flow during tattooing can mean more ink washout before macrophages lock the pigment particles in place. Some artists report that numbed skin heals with muted colour or blurred lines, and this observation is consistent with what vasodilation would predict, but it has not been quantified in a controlled study.
Q: How long before a tattoo should I apply numbing cream?
Most lidocaine-based creams require 30 to 45 minutes of contact time under occlusion (cling film) to penetrate the intact stratum corneum. Applying it 10 minutes before the needle hits does almost nothing, because the drug has not reached the dermal nerve endings. If you do apply it, follow the manufacturer's timing instructions, and remove it completely with a clean damp cloth before the artist begins skin preparation. Do not reapply mid-session onto broken skin.
Q: Is numbing cream legal for tattoo artists to use?
It depends on the jurisdiction. In Oregon, as of April 2026, artists are explicitly prohibited from applying numbing products to clients. In the EU, lidocaine is a prescription-only medicine, meaning an artist supplying or applying it is practising medicine without a licence. In most US states without an explicit ban, the legal status is grey: the product is legally sold OTC to consumers, but an artist applying it to a client's skin before a procedure may be interpreted as unlicensed drug administration. If you are an artist, the safest position in any jurisdiction is to let the client purchase and apply their own cream and to document that you did not supply, apply, or instruct on its use.
Q: Can numbing cream cause an allergic reaction?
Yes, though true IgE-mediated allergy to amide anaesthetics (lidocaine, prilocaine) is rare. Ester-type anaesthetics (benzocaine, tetracaine) have a higher sensitisation rate. More common are irritant contact reactions to the cream base (preservatives, fragrances, propylene glycol) rather than to the active ingredient. A client who has never used a numbing product before should patch-test a small area of intact skin 24 to 48 hours before using it on the area to be tattooed. An allergic reaction on top of a fresh tattoo complicates healing and increases infection risk.
Q: What should I do if a client shows signs of lidocaine toxicity during a session?
Stop the session immediately. Early signs include tinnitus (ringing in the ears), a metallic taste, lightheadedness, and numbness or tingling around the mouth that was not present before the cream was applied. Wipe any residual cream from the skin. Keep the client seated or lying down. If symptoms are mild and resolve within minutes, the client should still be advised to seek medical evaluation, because CNS symptoms can precede cardiovascular symptoms. If symptoms progress (confusion, slurred speech, muscle twitching, drowsiness) or if cyanosis (blue-grey skin, particularly lips and nail beds) appears, call emergency services and state clearly that you suspect local anaesthetic systemic toxicity. Methylene blue is the antidote for methemoglobinemia, and lipid emulsion is used for severe lidocaine cardiac toxicity; both require hospital administration.
Also compare
- Piercing Pain Guide, pain expectations by placement - Medication Interaction Checker, cross-check client prescriptions - Client Health Screening Tool, pre-procedure safety checklist - Reaction Triage Wizard, when something goes wrong during a session - Oregon Just Nuked Topical Numbing for Tattoo Artists, regulatory deep-dive - Wound Healing Biology, the science behind skin repair - Healing Tracker, monitor healing progress after the session - Keloid/Scar Risk Tool, scar risk assessment6. Can You Apply Numbing Cream During a Tattoo?
Most numbing creams are designed for pre-tattoo application, but clients often ask if they can reapply mid-session. The short answer: it depends on the product, but in most cases, you shouldn't. Here's why.
Most topical anaesthetics contain lidocaine or prilocaine in concentrations that are safe when applied to intact skin for a limited time. During a tattoo, the skin is broken, the needle has created thousands of micro-openings. Reapplying cream then can lead to systemic absorption far faster than intended, increasing the risk of lidocaine toxicity and methemoglobinemia, a condition where your blood can't carry oxygen effectively. I've seen clients pass out from this, it's not the same as the brief light-headedness of pain; it's a medical emergency.
Also, numbing cream changes skin texture. It can make the skin waxy or slippery, which affects how the needle tracks and how evenly the ink deposits. If you're mid-line and the skin suddenly feels different, the artist has to adjust, and that can lead to patchy healing or blowouts. Over-application can also cause vasoconstriction (narrowing of blood vessels), which reduces blood flow to the area and can alter how the ink settles.
So what should you do if pain becomes unbearable mid-session? First, tell your artist. They may have a tattoo-safe numbing spray containing a lower concentration of lidocaine, designed specifically for broken skin, but even that should be used sparingly and only after checking the label for "safe on broken skin" or similar. Never bring your own cream from home and assume it's fine. The risk isn't worth it.
If your artist doesn't offer a safe alternative, the best option is to take a break. Some shops allow split sessions, get the outline, heal, and book a second appointment for shading or color. That's a better outcome than ending up in the ER or with a ruined piece.
Bottom line: numbing cream before a tattoo is a tool, not a toy. Use it correctly for the initial numbing, and trust your artist for the rest. If you're preparing for a session, or you're an artist looking for safe aftercare and jewelry options, I’ve written extensively on body-safe products. Check out our guide to BioFlex® and polymer jewelry for what goes in your piercing after it's healed.
— Patrick Poli
6. Can You Apply Numbing Cream During a Tattoo? What I Allow and Why
The short answer: yes, a qualified artist can apply a topical anaesthetic during a session — but only under specific conditions. The longer answer matters more, because the query "can you apply numbing cream during a tattoo" hides a split between two very different products. Pre-procedure creams — the 5% lidocaine types sold for cosmetic use — are designed for intact skin and a fixed onset window. Once the skin is broken by needles, you're in a different pharmacological situation. Most manufacturers' instructions explicitly say do not apply to broken skin. Artists who ignore that are improvising with your safety.
If I allow anything mid-session, it's a secondary numbing gel formulated for open skin — not the same tube you used at home. Even then, I apply it sparingly, blot it, and let it sit for the minimum time needed. The reason is practical: excess product changes how the skin feels under the needle, and it can drag pigment into the dermis unevenly. I've seen healed tattoos with patchy saturation that traced back to a mid-session cream applied too thickly.
Can you use lidocaine before a tattoo? Also yes, with caveats. Lidocaine is the active ingredient in most numbing creams, and it's effective — but it's not risk-free. The real concern is methemoglobinemia, a blood condition that reduces oxygen delivery. It's rare at OTC concentrations, but it becomes more likely with large surface areas, repeated application, or use alongside other anaesthetics. EMLA cream and tattoos is a search I see often, and the answer is the same: EMLA contains both lidocaine and prilocaine, and prilocaine is the more common trigger for methemoglobinemia. That doesn't make it forbidden — it makes it a decision you make with full information, not a casual squeeze from a tube.
Can you use numbing cream before tattoo fading treatments? Same logic applies, but with more caution. Fading treatments — whether saline or laser-adjacent — already stress the skin. Adding a vasoconstrictor or anaesthetic that alters blood flow can complicate the healing response. I tell clients to skip it unless a clinician prescribes it.
Here's my position after 25 years: I don't ban numbing cream, but I don't treat it as neutral. If you want to use it, bring it to your artist before the appointment. Read the label. Check for prilocaine. Don't wrap it under plastic for hours. And if you're tattooing a large area, talk to a pharmacist first — not a forum. Safety isn't the enemy of a good tattoo. It's what lets you enjoy it after the wrap comes off.
→ Read the full BioFlex® polymer safety standards or browse aftercare tools before your next session.


