Shop
Clinical Physics

Psoriasis and Tattoos: Clinical Safety Guide

PP

Chief Engineer

Patrick Poli

Journal Date

2026-07-14

Last Reviewed

2026-10-17

Why This Question Matters

Asking whether you can get a tattoo with eczema or psoriasis is not a cosmetic question. It is a clinical risk assessment at the intersection of dermatology, wound healing, and immunology. The answer depends on your specific condition, its current activity, the body location, and your willingness to manage risk before and after the procedure.
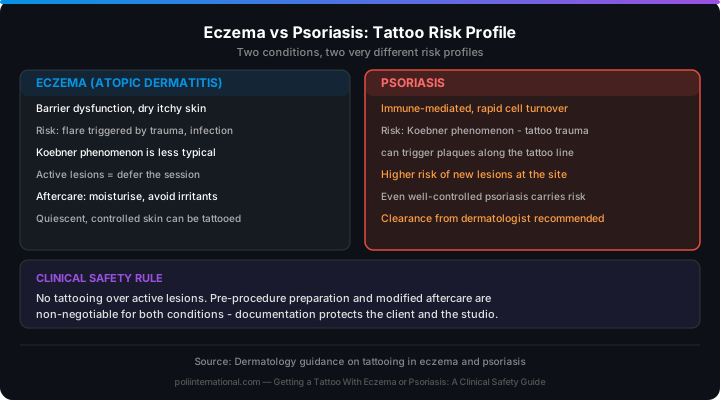
Eczema vs psoriasis tattoo risk profile comparison and clinical safety rules
Infographic: Eczema vs psoriasis tattoo risk profile comparison and clinical safety rules

Two Conditions, Two Risk Profiles

Eczema and psoriasis are both chronic inflammatory skin conditions, but they interact with tattooing in fundamentally different ways.

Psoriasis and the Koebner Phenomenon. The central risk for psoriasis is the Koebner phenomenon: new plaques developing at sites of skin trauma. Tattooing delivers thousands of needle punctures per minute into the dermis, precisely the kind of controlled trauma that can trigger this isomorphic response. Koebnerisation can appear within days or weeks, producing raised, scaly plaques directly along the tattoo lines that distort the design and may persist indefinitely. If you have never experienced Koebnerisation from cuts or surgery, your risk may be lower, but a first episode triggered by a tattoo is a documented outcome.

Atopic Dermatitis and the Barrier Problem. Eczema does not produce classical Koebnerisation. The risk instead stems from impaired barrier function caused by reduced filaggrin expression and altered stratum corneum lipids. Eczematous skin is more permeable to irritants, more prone to Staphylococcus aureus colonisation, and more reactive to minor stimuli. The primary concern is that tattooing triggers a systemic flare, potentially across body areas far from the tattoo site. A secondary concern: people with atopic dermatitis have higher rates of contact allergen sensitisation, including to metals and preservatives in tattoo inks.

Eczema vs Psoriasis: Risk Profile Comparison

Risk FactorEczema (Atopic Dermatitis)Psoriasis
Primary MechanismBarrier dysfunction, systemic flare riskKoebner phenomenon (isomorphic response)
Triggered ByIrritants, allergens, skin trauma, stressSkin trauma, streptococcal infection, stress
Tattoo-Specific RiskFlare at and beyond tattoo site; ink allergen reactionNew plaques along tattoo lines; design distortion
Koebner RiskNot a classical Koebner conditionCentral risk; estimated 25-75% prevalence
Ink Allergy ConcernElevated (higher baseline sensitisation rates)Baseline population risk
Healing ConsiderationImpaired barrier yields slower healing, higher infection riskNormal healing unless plaque develops at site

When It Is Safe, and When It Is Not

Definite Contraindications. Do not proceed with an active flare at or distant from the tattoo site. Do not proceed on systemic immunosuppressants (methotrexate, cyclosporine, biologics, systemic corticosteroids) without explicit dermatologist clearance. Do not proceed during phototherapy or while on systemic retinoids, or within 6-12 months of discontinuing them.

Relative Contraindications. A history of Koebner phenomenon elevates risk. If you proceed, begin with a small 2-3 cm test tattoo in a discreet location and observe for 6-8 weeks. Multiple contact allergies warrant ink composition disclosure from your artist. Facial and neck locations carry higher stakes if triggered.

Likely Safe. Psoriasis in stable remission for 3-6 months without Koebner history. Mild, well-controlled eczema with the tattoo site clear and intact for weeks. A test tattoo with adequate observation before the full piece is the most conservative approach.

Pre-Procedure Preparation

Get written clearance from your dermatologist, who can assess disease state, review medications, and identify risks no tattoo artist is trained to evaluate. Stabilise the skin barrier for at least 4 weeks with consistent fragrance-free emollient use; discuss with your dermatologist whether to pause prescription topicals at the site in the week prior. Avoid known triggers: food triggers, allergens, and stress for eczema; streptococcal infections, alcohol, and smoking for psoriasis. If you have contact allergies, request ink samples for dermatologist patch testing 48-72 hours before. Disclose your full diagnosis, medications, and allergies to your artist. They may decline, and that refusal is a professional risk assessment you should respect.

Aftercare Modifications

Standard aftercare assumes normal skin. For eczema and psoriasis, use breathable dressings and remove sooner if itching develops. Cleanse with a soap-free emollient wash rather than true soap. Begin fragrance-free emollient from day 1-2, using only previously tolerated products. Manage itch with cold compresses; oral non-sedating antihistamines may help. If a flare develops adjacent to the tattoo, apply prescription topicals to the flared area only. Cover with clothing during the full 6-week healing period; use SPF 50+ thereafter. Monitor for new psoriasis plaques at the tattoo margin, spreading eczema, and delayed hypersensitivity reactions appearing 7-14 days post-procedure.

Ink Chemistry and Allergic Skin

Tattoo inks contain pigments, carriers, and manufacturing contaminants. For sensitised individuals, known risks include nickel, cobalt, and chromium as trace contaminants in iron-oxide and titanium-dioxide pigments; PPD in some black inks; colophony as a binder; and formaldehyde-releasing preservatives. The highest-yield step: request brand and colour codes from your artist, then obtain allergen declarations or safety data sheets from the manufacturer. A manufacturer unwilling to disclose pigment composition is a red flag.

Key Takeaways

» Psoriasis and eczema are different conditions with different tattooing risk profiles: Koebner phenomenon for psoriasis, barrier failure and systemic flare risk for eczema.

» Active disease, systemic immunosuppressant therapy, and systemic retinoid therapy are strong contraindications to tattooing.

» A dermatologist consultation with written clearance is the single most important pre-tattoo step for anyone with a chronic inflammatory skin condition.

» A small test tattoo followed by 6-8 weeks of observation is the most rigorous safety approach.

» Modified aftercare, including earlier emollient use, soap-free cleansing, and vigilant monitoring for delayed reactions, is non-negotiable.

» Ink composition disclosure and patch testing matter more for sensitised immune systems than for the general population.

Patrick's Deep Archive

I have spent over twenty-five years in the materials and clinical safety side of body modification, and I have watched the gap between what dermatology knows and what tattoo studios practise persist. In the 1990s, artists either turned away anyone who mentioned psoriasis or proceeded with no risk assessment. Neither extreme served clients.

The Koebner phenomenon is real, and I have seen it happen. I have also seen people with well-controlled psoriasis sit for full sessions with excellent results and no complications. The difference was never luck. It was preparation, dermatologist involvement, and honest risk stratification. The question is not "can I get a tattoo?" but "under what conditions is it reasonable, and what am I willing to do to manage the risk?" That is how we approach materials certification, needle geometry, and aftercare protocol design at Poli International.

If I had to distil a quarter-century of clinical observation into one piece of advice: your tattoo artist is not your dermatologist, and your dermatologist is not your tattoo artist. You need both, and they need to be aware of each other. The best outcomes involve a three-way conversation between patient, prescribing dermatologist, and informed artist. That is the standard to aim for.

Frequently Asked Questions

Can tattooing cause psoriasis if I have never had it before?

Tattooing does not cause psoriasis in someone without genetic predisposition. Psoriasis has a strong hereditary component (HLA-Cw6 association), and the Koebner phenomenon unmasks it in susceptible individuals rather than creating it de novo. If psoriasis appears for the first time after a tattoo, the tattoo was the trigger, not the cause.

Can I use my prescription eczema cream on a healing tattoo?

Not without specific dermatologist instruction. Topical corticosteroids applied to a healing tattoo can impair wound healing and alter pigment retention. If a flare develops adjacent to the tattoo, apply medication to the flared area only, keeping it off the tattoo itself. Calcineurin inhibitors may be safer than corticosteroids on healing skin, but this is a clinical decision for your dermatologist.

How long should I wait after a psoriasis flare clears?

Most dermatologists recommend 3-6 months of disease stability. Psoriasis flares involve systemic immune activation that persists after visible plaques resolve. Six months is conservative; three months may be acceptable for mild disease without Koebner history. Your dermatologist sets this timeline.

Can I get a tattoo on dupilumab for eczema?

Dupilumab blocks IL-4 and IL-13 with more targeted immunosuppression than traditional systemic agents. Surgical wound-healing data is reassuring, but tattoo-specific safety data does not exist. If your eczema is well-controlled and your dermatologist clears you, tattooing may be reasonable with the same test-tattoo and modified-aftercare precautions.

Do the same rules apply to piercings?

Partially. The Koebner phenomenon applies to piercings as puncture wounds. Dermatologist clearance is equally important. However, piercings create a smaller wound surface with different healing biology (fistula formation versus pigment encapsulation). Metal allergy, particularly nickel, is relevant to piercings. See our material certification checker to verify jewellery composition.

Conclusion

Getting a tattoo with eczema or psoriasis is a calculated risk. The determinants of your outcome are disease stability, medication status, Koebner history, ink chemistry, and the quality of your preparation and aftercare. A dermatologist consultation with written clearance is the single most important step. A test tattoo with adequate observation is the most rigorous safety approach. Modified aftercare is non-negotiable. Tattoos are permanent, and so is a psoriasis plaque triggered in the middle of one. Decide with the full clinical picture in view.

- Health Conditions and Tattoo Contraindications -- medical conditions affecting tattooing safety
- Keloid-Prone Tattoo Safety -- scarring risk assessment for body modification
- Aftercare Science -- evidence-based wound healing protocols
- Accutane/Isotretinoin and Tattoo Safety -- retinoid therapy and body modification risk
- Needle Geometry and Dermal Recovery -- how needle configuration affects wound healing
- Reaction Triage Wizard -- identify whether a post-procedure skin reaction needs attention
- Keloid Scar Risk Evaluator -- assess personal scarring risk before a procedure
- Wound Healing Biology -- the science of skin healing
- Metallic Biocompatibility -- implant-grade materials and skin compatibility

6. Psoriasis and Tattoo Aftercare: What Changes

If you have psoriasis and decide to get a tattoo, aftercare is not just about keeping the ink clean—it's about managing your skin's inflammatory response. Standard aftercare instructions assume healthy skin that heals predictably. With psoriasis, you're dealing with an immune system that may overreact to the trauma of tattooing, potentially triggering new lesions (Koebner phenomenon) or delaying healing. I've seen clients with well-managed psoriasis who healed beautifully, but only because they followed a modified protocol that respected their condition.

First, talk to your dermatologist before booking. If you're on immunosuppressants like Cosentyx, you need to know if that medication affects wound healing or increases infection risk. Some biologics may require a pause around the tattoo session—but never stop or adjust medication without medical supervision. I'm not a doctor, and I won't pretend to be one. I've been in this industry for 25 years, and I've learned that the safest approach is to have your dermatologist sign off on the plan.

Once you have clearance, here's what changes in aftercare:

- Keep it clean but gentle. Use a mild, fragrance-free cleanser—nothing with exfoliants or acids. Pat dry, never rub.
- Moisturize more frequently, but avoid heavy occlusives. Thick ointments can trap heat and sweat, which can irritate psoriatic skin. Instead, use a lightweight, hypoallergenic lotion several times a day.
- Watch for plaque formation. If you see scaling or raised areas developing at or around the tattoo, that's not a normal healing sign—it could be a Koebner response. Contact your dermatologist immediately.
- Avoid sun exposure on the tattoo until fully healed. UV light can both help and worsen psoriasis depending on the individual, but on a fresh tattoo, it's just a risk factor.

Also, consider the jewellery you'll use if you're getting a piercing as part of your tattoo work. For clients with inflammatory skin conditions, I always recommend BioFlex®—our PP-R polymer jewellery is non-reactive, flexible, and free of nickel, which is a common trigger. You can find our full range at /bioflex/ and see why it's used by professionals who prioritize safety.

Remember: psoriasis doesn't automatically rule out tattoos, but it demands respect. Plan ahead, follow your dermatologist's advice, and give your skin time to heal without shortcuts. That's how you keep both your ink and your skin healthy.

Mind map · Psoriasis and Tattoos: Clinical Safety Guide

  • Chronic Skin Condition Tattoo Safety
    • Dermatologist Consultation

      A dermatologist consultation with written clearance is the single most important pre-tattoo step for anyone with a chronic inflammatory skin condition.

      • Dermatologist Written Clearance
      • Medication and Risk Review
    • Contraindications

      Active disease, systemic immunosuppressant therapy, and systemic retinoid therapy are strong contraindications to tattooing.

      • Active Skin Flares
      • Systemic Immunosuppressants
      • Oral Retinoids
    • Koebner Phenomenon

      The central risk for psoriasis is the Koebner phenomenon where new plaques develop at sites of skin trauma.

      • New Plaques Along Lines
      • Test Tattoo Observation
        • Observe For Six Weeks
    • Eczema Barrier Dysfunction

      Eczema risk stems from impaired barrier function, making skin more permeable to irritants and prone to Staphylococcus aureus colonisation.

      • Increased Infection Risk
      • Ink Allergen Reactions
        • Avoid Red Pigments
    • Modified Aftercare

      Modified aftercare, including earlier emollient use, soap-free cleansing, and vigilant monitoring for delayed reactions, is non-negotiable.

      • Soap-Free Cleansing
      • Fragrance-Free Emollients
      • Vigilant Infection Monitoring
StructureProcessMaterialHazard

5 branches, 0 sources. Each branch cites the article it came from; the labels beneath it are names, not claims.

Dermatology Quiz

  1. 1. What is the primary clinical mechanism through which tattooing risks triggering new psoriasis plaques along tattoo lines?

    • • Barrier failure caused by reduced filaggrin expression — Reduced filaggrin expression causes barrier dysfunction in eczema, rather than causing new psoriatic plaques.
    • ✓ Isomorphic response known as the Koebner phenomenon — The Koebner phenomenon involves new psoriatic plaques developing directly at sites of controlled mechanical skin trauma like needle punctures.
    • • Systemic IgE-mediated hypersensitivity to titanium dioxide — Titanium dioxide sensitivities relate to contact allergies or pigment contaminants rather than the primary mechanism of psoriasis plaque formation.
    • • Delayed vascular proliferation triggered by heavy occlusives — Heavy occlusives can trap heat and irritate skin, but they do not cause the characteristic isomorphic reaction of psoriasis.
  2. 2. What structural skin abnormality primarily accounts for impaired barrier function and increased permeability in clients with atopic dermatitis?

    • • High concentration of colophony binders in the epidermis — Colophony is a binder used in tattoo inks rather than an innate structural component of human epidermal tissue.
    • ✓ Reduced filaggrin expression and altered stratum corneum lipids — Lower levels of filaggrin and altered lipids in the outer skin layer increase permeability and vulnerability to external irritants.
    • • Uncontrolled systemic activation of HLA-Cw6 genes — HLA-Cw6 is a hereditary genetic marker associated with psoriasis predisposition rather than eczema barrier dysfunction.
    • • Dermal encapsulation failure of titanium dioxide pigments — Pigment encapsulation failure relates to ink retention issues rather than the primary barrier defect of eczema.
  3. 3. According to clinical guidelines, how long after discontinuing systemic retinoids must a client wait before tattooing is considered safe?

    • • 2 to 4 weeks — A 2 to 4 week window is insufficient for skin recovery following systemic retinoid therapy.
    • • 6 to 8 weeks — A 6 to 8 week period is the observation timeframe following a test tattoo, not the post-retinoid waiting period.
    • • 3 to 5 months — A 3 to 5 month timeline does not satisfy the full conservative clinical requirement for post-retinoid recovery.
    • ✓ 6 to 12 months — Systemic retinoids significantly alter skin healing biology and require a strict waiting period of 6 to 12 months post-discontinuation.
  4. 4. If a client with a history of Koebner phenomenon decides to proceed with a tattoo, what initial protocol is recommended to evaluate personal risk?

    • • Apply a topical corticosteroid to the target area for 14 days before tattooing — Topical corticosteroids should not be applied preemptively as they can alter wound healing and pigment retention.
    • ✓ Perform a 2-3 cm test tattoo and observe it for 6-8 weeks — A small test tattoo combined with a 6 to 8 week observation period allows monitoring for an isomorphic response before committing to a larger piece.
    • • Get a single-pass full session using only iron-oxide based pigments — Proceeding with a full session exposes the client to widespread trauma without establishing whether Koebnerisation will occur.
    • • Undergo phototherapy immediately prior to receiving the full tattoo piece — Active phototherapy is listed as a definite contraindication for receiving a tattoo.
  5. 5. How long should a client with eczema or psoriasis consistently use fragrance-free emollients before a tattoo procedure to stabilize the skin barrier?

    • ✓ At least 4 weeks — A 4-week commitment to fragrance-free emollients helps strengthen and stabilize barrier function prior to controlled skin trauma.
    • • 48 to 72 hours — The 48 to 72 hour window is used for dermatologist patch testing of ink samples, not skin barrier stabilization.
    • • 7 to 14 days — One to two weeks is too brief to achieve adequate barrier stability in compromised skin.
    • • At least 6 months — Six months represents the upper stability window required after a psoriasis flare resolves, rather than the emollient prep time.
  6. 6. If an inflammatory flare develops adjacent to a healing tattoo, how should prescription topical medications be applied?

    • • Apply topical corticosteroids directly over the healing tattoo to prevent pigment loss — Topical corticosteroids applied directly to a healing tattoo can impair wound healing and alter pigment retention.
    • ✓ Apply the prescription topical strictly to the flared area, keeping it off the healing tattoo — Restricting medication strictly to the adjacent flared skin treats the inflammatory response without disturbing pigment encapsulation.
    • • Pause all moisturizers and double the dosage of systemic immunosuppressants — Systemic medication adjustments must only be made under medical supervision, and pausing moisturizers worsens barrier failure.
    • • Mix the prescription cream into a heavy occlusive ointment and cover the entire area — Heavy occlusives trap heat and sweat, which can exacerbate skin inflammation and disturb fresh ink.
  7. 7. Which specific metals are highlighted as trace contaminants in iron-oxide and titanium-dioxide tattoo pigments?

    • • Gold, silver, and platinum — Precious metals like gold and silver are not standard contaminants in titanium-dioxide or iron-oxide pigments.
    • ✓ Nickel, cobalt, and chromium — Nickel, cobalt, and chromium frequently appear as trace contaminants in common pigment oxides and pose significant contact allergy risks.
    • • Zinc, copper, and aluminum — Zinc and copper are not highlighted as the primary trace allergens found within these pigment categories.
    • • Lead, mercury, and arsenic — Heavy metals like lead and mercury are not identified in the source text as the key trace allergens in iron-oxide formulations.
  8. 8. When monitoring a new tattoo on sensitised skin, during what timeframe do delayed hypersensitivity reactions typically manifest?

    • • 1 to 3 hours post-procedure — Immediate hours post-procedure reflect acute mechanical trauma rather than delayed immunological hypersensitivity.
    • • 24 to 48 hours post-procedure — The 24 to 48 hour window represents standard acute swelling rather than delayed cell-mediated sensitisation.
    • ✓ 7 to 14 days post-procedure — Delayed cell-mediated hypersensitivity responses to tattoo ink ingredients typically take 7 to 14 days to appear.
    • • 6 to 8 months post-procedure — Six to eight months is well beyond the typical timeline for initial delayed hypersensitivity reactions.
  9. 9. How does tattooing interact with psoriasis in individuals who have never previously exhibited symptoms of the condition?

    • • Tattoo ink alters normal cellular DNA to generate psoriasis de novo — Tattooing does not create psoriasis de novo without an existing genetic foundation.
    • ✓ Controlled skin trauma can unmask psoriasis in individuals with a genetic predisposition — Physical skin trauma from needles acts as an environmental trigger that unmasks psoriasis in genetically susceptible individuals.
    • • Needle punctures destroy filaggrin expression, inducing non-hereditary psoriasis — Filaggrin deficiency is central to atopic dermatitis, not the mechanism of unmasking psoriasis.
    • • Psoriasis develops only if the tattoo artist uses formaldehyde-releasing preservatives — Formaldehyde preservatives can cause allergic contact dermatitis, but they do not cause genetic psoriasis.
  10. 10. Why is BioFlex® (PP-R polymer) recommended for body piercings in clients with chronic inflammatory skin conditions?

    • • It actively releases systemic corticosteroids directly into the piercing fistula — Body modification jewellery does not contain or secrete prescription corticosteroid medications.
    • ✓ It is non-reactive, flexible, and free of nickel triggers — PP-R polymer provides a flexible, highly biocompatible alternative that eliminates exposure to nickel allergens.
    • • It permanently prevents the Koebner phenomenon from occurring on any body area — No jewellery material can globally prevent Koebner responses induced by skin trauma elsewhere.
    • • It dissolves after 6 weeks to eliminate long-term jewellery maintenance — Piercing jewellery is designed to maintain fistula patency rather than dissolve during healing.

Extended Reference Table

8 of 8 rows

Extended reference table generated from the article and its verified research sources. Bracketed numbers jump to the matching entry in the Technical References below.

SafetyItem, Material, or Practice Condition or Scope Clinical Risk or Mechanism Standard, Compliance, or Specification Recommended Action or Contraindication Source
⚠️TattooingPsoriasisKoebner phenomenon (isomorphic response); needle trauma induces new plaques at injury sites in 25–30% of patients.HLA-Cw6 genetic association; Clinical dermatology guidelinesContraindicated during active flares; require 3-6 months stability; avoid known plaque sites.
⚠️Isotretinoin / Systemic RetinoidsActive Acne or Psoriasis TreatmentDelayed wound healing, skin fragility, and increased risk of atypical scarring during re-epithelialization.FDA drug labeling; Clinical consensusAbsolute contraindication; wait 6-12 months after cessation before tattooing.
✅Biologic Agents (TNF-alpha, IL-17, IL-4/13 inhibitors)Chronic Inflammatory Conditions (Eczema/Psoriasis)Immunosuppression leading to increased risk of secondary bacterial or atypical mycobacterial infections.British Association of Dermatologists guidelinesDo not stop medication; coordinate timing with dosing cycles and seek dermatologist clearance.
⚠️TattooingAtopic Dermatitis (Eczema)Barrier dysfunction (reduced filaggrin) and S. aureus colonization increase infection and systemic flare risk.National Eczema Association; Dermatology (MeSH)Contraindicated during active flares; stabilize skin barrier for 4 weeks with emollients prior to procedure.
✅Implant-grade TitaniumNickel Allergy / Contact DermatitisExposure to nickel in jewelry triggers allergic contact dermatitis in sensitized individuals.ASTM F136Strictly required for patients with known nickel allergies; use as starter pieces to minimize reactivity.
✅Tattoo Pigments / InksContact Allergen SensitizationType IV delayed hypersensitivity to metals (nickel, cobalt, chromium) or azo dyes (PPD).Manufacturer Safety Data Sheets (SDS)Request brand/color codes for dermatologist patch testing 48-72 hours before tattooing; avoid red-spectrum inks.
✅MethotrexateSystemic Psoriasis / Arthritis TreatmentAffects cell division and suppresses immune function, potentially slowing wound healing.Clinical Dermatology standardsConsult a physician regarding treatment timing; do not stop unilaterally to avoid rebound flares.
✅Topical CorticosteroidsEczema and Psoriasis ManagementSkin thinning (atrophy) which may affect ink deposition depth and impair wound healing.Clinical Dermatology standardsDo not apply directly to a healing tattoo or piercing; apply only to adjacent flared areas if necessary.

Free Body Art Wall Posters

Print-ready reference posters for your studio or your own wall. Free to download and display, embed on your own site with attribution. Click any poster to preview it full size before downloading.

Choose and download all 40 posters

Technical_References_Archive

About the Author

PP

Patrick Poli

Chief Engineer, Poli International · Creator of BioFlex® body jewelry

Patrick has spent 25+ years manufacturing body jewellery and studio equipment, and is the creator of BioFlex® body jewelry. He created the push-fit system so jewellery separates on impact instead of tearing the piercing. He also designed the flexible belly bar that lets a navel piercing stay in place through a pregnancy.

More about Patrick →

Last reviewed: 2026-10-17 · Published: 2026-07-14

Continue Reading
