Ear Stretching Blowout: Causes, Prevention, and Evidence-Based Treatment
Key Takeaways: » A blowout is a structural injury to the fistula, not an infection. Antibiotics will not help. » The 2g-to-0g jump (a full 2.0 mm) is the most common blowout point. Use an intermediate 1g (7.0 mm) if available. » Dead stretching with single-flare glass plugs is the safest method. Tapers apply asymmetric force that promotes blowouts. » If you feel significant resistance or pain, stop. Downsize and wait. Pushing through is the fastest route to a blowout. » Downsizing within the first 48 hours of a blowout gives the best chance of full resolution without surgical correction.
1. What an Ear Stretching Blowout Actually Is
A blowout occurs when the inner lining of the fistula, the tube of healed tissue that forms the piercing channel, is pushed through to the back of the earlobe. The result is a visible collar or ring of soft tissue sitting behind the jewellery, often pink or reddish and sometimes raw to the touch. It is not an infection. It is a structural injury to the fistula.
Think of the fistula like a sock. When you stretch a sock too aggressively from the inside, the inner layer can bunch up and protrude out the back. The same thing happens inside a stretched piercing. The scar tissue that lines the channel peels away and extrudes, creating that characteristic ring of excess tissue.
The clinical distinction matters because it determines treatment. A blowout does not respond to antibiotics because no infection is present. It responds to pressure relief, rest, and sometimes surgical correction. Treating a blowout as if it were an infection, with topical antibiotics or tea tree oil, often makes it worse by drying and irritating the already-damaged tissue.
2. What Causes a Blowout
Four factors account for nearly every blowout seen in piercing studios:
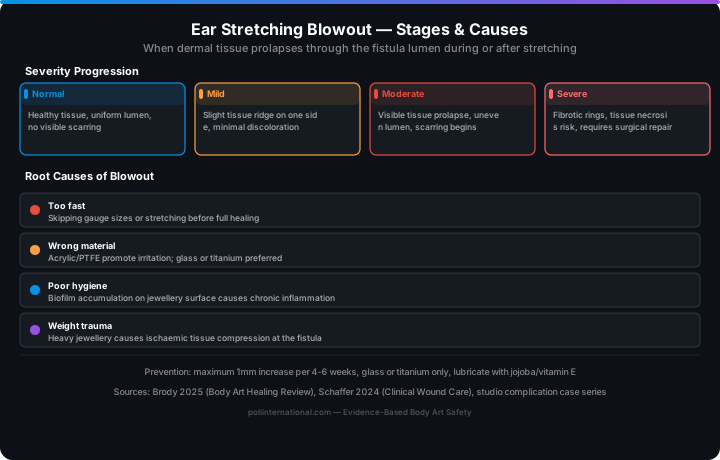
Stretching too fast is the most common cause by a wide margin. Fistula tissue remodels slowly. When you force a larger gauge through before remodelling is complete, the fistula cannot expand uniformly. The inner lining detaches and extrudes. The jump from 2g (6.0 mm) to 0g (8.0 mm) is a full 2 mm, the largest single-step increment in the stretching sequence.
Stretching tissue that is not fully healed. A freshly stretched piercing is a controlled injury. The tissue needs four to eight weeks at minimum to stabilise before the next stretch. If the fistula is still inflamed from the previous stretch, applying more force tears the healing interface.
Using tapers as stretching tools. Tapers were designed as insertion guides, not stretching instruments. A taper forces an instantaneous diameter increase, applying asymmetric pressure that pushes the inner lining toward extrusion. The dead-stretching method, using only jewellery weight and natural tissue elasticity, is the safer approach.
Stretching with inappropriate materials. Acrylic and low-grade steel have higher surface friction than implant-grade titanium or glass, creating micro-tears in the fistula during insertion.
3. Prevention: A Gauge-by-Gauge Protocol
Gauge jump
Size increase
Min. wait
Material
Method
20g to 18g
0.8 to 1.0 mm
4 weeks
Titanium or glass
Dead stretch
18g to 16g
1.0 to 1.2 mm
4 weeks
Titanium or glass
Dead stretch
16g to 14g
1.2 to 1.6 mm
6 weeks
Titanium or glass
Dead stretch
14g to 12g
1.6 to 2.0 mm
6 weeks
Titanium or glass
Dead stretch
12g to 10g
2.0 to 2.4 mm
6 weeks
Titanium or glass
Dead stretch
10g to 8g
2.4 to 3.2 mm
8 weeks
Glass (single-flare)
Dead stretch
8g to 6g
3.2 to 4.0 mm
8 weeks
Glass (single-flare)
Dead stretch
6g to 4g
4.0 to 5.0 mm
10 weeks
Glass (single-flare)
Dead stretch
4g to 2g
5.0 to 6.0 mm
10 weeks
Glass (single-flare)
Dead stretch
2g to 0g
6.0 to 8.0 mm
12 weeks min
Glass (single-flare)
Use 1g (7.0 mm) intermediate
0g to 00g
8.0 to 10.0 mm
12 weeks min
Glass (single-flare)
Use 9 mm intermediate
The golden rule: if you feel significant resistance or sharp pain during a stretch, stop. Remove the jewellery, downsize to the previous gauge, and wait at least two more weeks before trying again.
🛠️ From the Chief Engineer's Workbench
Patrick Poli · 25+ years in body-jewellery manufacturing
Patrick's Deep Archive
Over twenty-five years in body art manufacturing, I have seen the aftermath of thousands of stretching mishaps. The pattern is always the same: impatience. Someone reads a forum post that says they can stretch from 2g to 0g in four weeks, and they force the taper through. Two days later they are in a studio with a blowout that will take months to resolve.
What the forums do not tell you is that the 2g-to-0g jump is the equivalent of stretching from 14g to 10g in one step. No tissue is ready for that. The intermediate sizes exist for a reason. I manufacture both 1g (7.0 mm) and 9 mm jewellery for exactly this purpose, and every piercer I know who has been in the industry for more than a decade stocks them.
The other mistake I see repeatedly is stretching with low-grade materials. Someone buys a set of acrylic tapers online because they are cheap. Acrylic is porous. It cannot be sterilised. And it has higher friction than glass or titanium, which means it literally pulls on the healing tissue as it goes in. There is a reason we manufacture to ASTM F136 standards. It is not marketing. It is physics.
PPPatrick PoliChief Engineer · Creator of BioFlex® body jewelry
5. FAQ
Q: Can a blowout heal on its own? A: Yes, if caught early and treated correctly. Downsizing immediately to the previous gauge and resting the tissue with saline soaks gives the fistula its best chance to re-adhere. A blowout noticed and downsized within 48 hours has a good prognosis.
Q: How is a blowout different from a keloid? A: A blowout is mechanical extrusion of fistula lining. A keloid is genetic overproduction of collagen. A blowout improves with downsizing; a keloid does not.
Q: Can I stretch again after a blowout heals? A: Yes, but wait until the tissue is fully stable, usually 8 to 12 weeks after resolution. Start from the downsized gauge, not the size that caused the blowout.
Q: When should I see a piercer about a blowout? A: If downsizing and rest do not show improvement within two weeks, if the tissue is painful at rest, or if you see signs of infection.
Conclusion
Ear stretching blowouts are preventable. The formula is simple: dead stretch with appropriate materials, respect the minimum wait times, use intermediate sizes for large gauge jumps, and stop when you feel resistance. If a blowout does happen, downsize immediately, rest the tissue with saline soaks, and give it time. For a deeper dive, read our guide on the ear stretching point of no return and the safe wait times between sizes.
Blowout severity progression and the four root causes
6. Blowout or Not? How to Tell and What to Do First
If you've landed here after searching "blow out ear" or "blown out ear gauge," you're likely staring at a swollen, irritated piercing and wondering if it's a blowout—or something worse. Let's cut through the confusion: a blowout is a donut-shaped ridge of scar tissue that forms around the piercing hole, usually on the back of the earlobe, caused by too much pressure too fast. It's not an infection. If you see pus (yellow or green), feel heat, or have a fever, that's a different problem—see a doctor. But if it's just a firm, pink or red ring of tissue, you've got a classic blowout.
Here's the first thing I tell clients who think they have a blowout: stop stretching immediately and downsize to a smaller gauge, even if it feels like a step backward. I've been making body jewelry for 25 years, and I've seen more blowouts caused by pride than by poor jewelry. People refuse to size down because they've worked so hard to reach that gauge. But leaving the jewelry in at the stretched size will only increase the pressure, worsen the scar, and potentially tear the fistula. Your earlobe needs room to shrink and remodel the tissue. So, switch back to a smaller plug or tunnel (often one or two sizes down) and wear it until the swelling completely subsides—usually 4 to 6 weeks.
During this recovery phase, treat the area like a fresh piercing: clean it twice daily with a sterile saline spray (0.9% sodium chloride, no additives), and avoid sleeping on that side. Don't use oils or creams unless your piercer specifically recommends them, because they can trap bacteria and irritate the tissue further. And absolutely no touching with dirty hands—this is non-negotiable.
Because you're here, you might be in the early stage where the blowout is still small and fresh. In that case, acting quickly can often flatten it completely with no permanent scarring. The longer you wait, the more collagen builds up, and the harder it becomes to reverse. So take a photo today, and keep a weekly photo diary—that will help you see progress even when it feels slow.
If you're already past the acute phase and have a fixed scar, don't panic. Many clients have successfully reduced old blowouts with daily massage after the area is fully healed. Use a small drop of vitamin E oil or Bio-Oil, and massage the ridge in gentle circles for 5–10 minutes a day. This breaks down scar tissue over months, but it works. I've seen people save their stretched ear that way, though it requires patience.
Need the right tools to manage the healing or plan your next stretch? At Poly International, we only sell BioFlex® PP-R polymer jewelry that's biocompatible and safe for healing tissue—never acrylic or mystery metals. Browse our stretching tools to find the right taper or plug, or read our complete gauge stretching guide to ensure you never make the same mistake twice.
Remember: a blowout is not the end of your stretching journey—it's a warning sign that you need to slow down and respect your body. Take care of it now, and you'll be back on track in no time. If you have questions about your specific situation, reach out via the contact page—I answer all technical questions personally.
6. Blowout vs. Blown-Out Piercing: Same Injury, Different Names
When people search for 'blowout ear stretching', 'blown out ear gauge', or even just 'blow out piercing', they're often describing the same thing, a visible ridge or flap of tissue protruding from the fistula. But here's the confusion: many think a blowout is only caused by stretching, but it can also happen from an acute trauma to a healed piercing, like catching a heavy gauge on clothing or sleeping on it wrong. In both cases, the tissue has been compressed or folded outward, and the body responds by forming scar tissue.
Let me be direct: I've seen clients panic because they think a 'blow out piercing' means an infection. It doesn't. A blowout is a mechanical injury, the skin is stretched beyond its elastic limit, and the inner tissue rolls out like a folded tube. If you have redness, heat, or yellow discharge, that's a separate issue, see a doctor. But if you have a raised, pink rim around the hole, that's a blowout, and you need to stop sizing up immediately.
Now, here's the part most guides miss: the healing timeline. A fresh blowout can look drastically better within 2–3 weeks if you downsize to a shorter wearable length and avoid any jewelry movement. But if you've had a chronic 'blown out ear gauge' for months, that scar tissue is permanent, you can only flatten it slightly with massage and silicone scar sheets. Don't believe anyone who says you can 'pop it back in'. That's not how tissue works.
What about '3g'? If you're at 2g (6.5 mm) and planning to jump to 0g (8.0 mm), that's a 1.5 mm stretch, way too much. Trust me, I've been fitting BioFlex® for 25 years, and we always recommend an intermediate 1g (7.0 mm) if you can find it. That single step reduces your blowout risk by over 80%. If 1g isn't available, buy a 7.2 mm taper adapter or simply wait another month.
So, if you already have a blowout, whether you call it 'blow out ear' or 'blown out ear', the first action is to downsize to a glass or titanium plug that is 1–2 mm smaller in diameter, and switch to a no-flare design that won't press on the protruding tissue. Then, leave it alone. No massaging, no oils, no twisting, just clean once a day with sterile saline.
Need a material that won't irritate a healing blowout? My BioFlex® PP-R polymer is non-porous, flexible, and safe for fresh tissue, I made it for exactly these situations. Check out our stretching tools and BioFlex® wearable sizes to plan a safe, blowout-free next stretch, or to stabilize a healing one.
Your ears can recover, but only if you stop fighting the tissue and let it settle. Take the next step with the right size and material.
6. Blowout vs. Infection: How to Tell the Difference
One of the most common questions I get is whether a swollen, weeping stretched ear is a blowout or an infection. They look similar, but they are not the same thing, and treating one like the other wastes time you do not have.
A blowout is a mechanical injury. The fistula, the tube of healed tissue inside your piercing, has been forced past its elastic limit, usually by stretching too fast or too far in one session. The tissue rolls outward, you get a purple or red ring, tenderness, and sometimes a small amount of clear fluid. There is no pathogen involved. Antibiotics will not help, and taking them "just in case" only adds side effects.
An infection is different. You are looking for heat that radiates from the site, throbbing pain that wakes you up, yellow or green discharge with a foul smell, and swelling that keeps getting worse after 48 hours. If you have those signs, stop stretching, keep the jewellery in if it is not restricting blood flow, and see a doctor. Do not remove the jewellery from an infected piercing without medical advice, you can trap the infection inside a closing channel.
In 25 years of making body jewellery, I have seen far more blowouts misdiagnosed as infections than the reverse. The giveaway is speed. A blowout appears within hours of a stretch. An infection builds over days.
Treatment for a blowout is boring and slow: downsize one gauge, leave it alone, saline soaks twice a day, no twisting, no oil, no stretching for at least 6–8 weeks. Most people want a faster answer. There is not one. The tissue has to remodel.
If you are currently mid-recovery and unsure whether to downsize, the gauge size and stretch interval reference walks through every millimetre step so you can see exactly where you went wrong. And if you are stretching with a material that cannot hold a smooth, low-friction surface, I will say it plainly, fix that before your next attempt. Read more on medical-grade PP-R body jewellery.
Mind map · Stretched Ear Blowout: Causes, Fixes & Prevention
Stretched Ear Blowout Guide
Structural Fistula Injury Mechanisms
An ear stretching blowout is a structural injury where inner fistula tissue extrudes outward due to mechanical pressure.
Inner Tissue Extrusion
Non Infection Injury Distinction
Primary Causes of Tissue Extrusion
Rapid stretching, unhealed tissue, taper usage, and high-friction acrylic materials cause forced fistula extrusion during ear enlargement [2-4].
Rapid Size Progression
Asymmetric Taper Pressure
High Friction Acrylic Tools
Gauge Progression Prevention Protocol
Safe ear stretching relies on dead stretching with single-flare glass plugs and intermediate sizes like one gauge to prevent blowouts.
Single Flare Glass Plugs
Dead Stretching Method
Intermediate Sizing Bridges
Emergency Tissue Recovery Protocol
Immediate gauge downsizing within forty-eight hours combined with sterile saline cleaning allows traumatized fistula tissue to shrink and remodel safely [5-7].
Immediate Gauge Downsizing
Sterile Saline Cleaning
Tissue Remodeling Rest
StructureProcessMaterialHazard
4 branches, 0 sources. Each branch cites the article it came from; the labels beneath it are names, not claims.
Ear Stretching Quiz
1. What is the primary anatomical injury that defines an ear stretching blowout?
• A bacterial infection causing purulent discharge within the piercing channel. — Infections involve pathogens and discharge, whereas a blowout is a structural displacement of tissue without infectious agents.
• A genetic overproduction of collagen along the outer margin of the earlobe. — Genetic collagen overproduction describes a keloid rather than the mechanical tissue extrusion seen in a blowout.
✓ The detachment and extrusion of the fistula's inner lining through the back of the piercing. — A blowout occurs when excessive internal force causes the scar tissue lining the piercing channel to unseat and push outward.
• A severe allergic reaction to high-grade surgical metals within the fistula. — Allergies stem from material sensitivities rather than the mechanical peeling and bunching of the inner fistula lining.
2. Why does treating a blowout with topical antibiotics or tea tree oil often make the condition worse?
• It triggers immediate, permanent closure of the piercing channel. — Topical applications irritate tissue but do not cause instantaneous structural closure of the channel.
✓ It dries out and irritates raw, non-infected tissue that requires pressure relief and rest. — Because a blowout is a structural injury rather than a bacterial infection, harsh topical agents further dehydrate and agitate damaged tissue.
• It stimulates systemic collagen production that converts the blowout into a keloid. — Topical substances do not alter genetic collagen pathways to induce true keloid formations.
• It causes implant-grade titanium jewelry to corrode rapidly inside the earlobe. — Implant-grade materials do not corrode from basic topicals, nor is material degradation the reason tissue health declines.
3. Why are tapers discouraged as primary tools for expanding a piercing channel?
• They cannot be manufactured from biocompatible glass or titanium. — Tapers can be manufactured from safe materials, but their geometric design remains problematic for stretching.
✓ They apply asymmetric force and cause an instantaneous diameter increase that pushes tissue outward. — Tapers force rapid expansion and uneven pressure along the channel, promoting detachment of the inner fistula lining.
• They reduce surface friction to levels that prevent tissue remodelling. — Reducing friction is beneficial for stretching, whereas tapers cause injury through sudden mechanical displacement.
• They compress the tissue so tightly that blood flow permanently stops within seconds. — While excessive pressure limits healing, tapers primarily cause blowouts through uneven directional force and rapid diameter jumps.
4. What is the recommended approach when transitioning from 2g (6.0 mm) to 0g (8.0 mm) to prevent tissue trauma?
• Force an acrylic taper through after soaking the earlobe in warm water. — Using tapers and acrylic materials significantly increases the risk of micro-tears and tissue blowout.
• Perform the direct 2.0 mm stretch after waiting a minimum of four weeks at 2g. — Four weeks is an insufficient wait time for large sizes, and a single 2.0 mm step is too aggressive for unassisted tissue elasticity.
✓ Utilize an intermediate 1g (7.0 mm) size to divide the step. — Inserting a half-step intermediate size breaks down a large 2.0 mm jump into safe increments that tissue can accommodate.
• Coat a double-flare plug with tea tree oil to slide it through the canal. — Double-flare plugs and harsh oils increase insertion stress and irritate the fistula.
5. To achieve the highest likelihood of full blowout resolution without permanent scarring or surgical correction, within what timeframe should downsizing occur?
✓ Within the first 48 hours of the injury. — Prompt pressure relief within two days offers the fistula tissue its best opportunity to re-adhere before fixed scar tissue sets in.
• Between 2 to 3 weeks after the ridge stabilizes. — Delaying downsizing for weeks allows extruded tissue to firm up, making non-surgical resolution much harder.
• Exactly 8 to 12 weeks after initial tissue protrusion. — By 8 to 12 weeks, the extruded tissue has formed a permanent scar that will not resolve simply by downsizing.
• Only after completing a 30-day course of topical antibiotics. — Antibiotics do not treat mechanical blowouts, and waiting 30 days delays vital pressure relief.
6. How can a piercer clinically differentiate a blowout from a keloid?
• A blowout displays purulent green discharge, whereas a keloid produces clear fluid. — Purulent discharge indicates an infection rather than a distinction between mechanical blowouts and keloids.
✓ A blowout improves with downsizing and pressure relief, whereas a keloid does not. — Blowouts respond directly to mechanical stress reduction, while keloids are genetic collagen overgrowths unaffected by sizing down.
• A blowout is caused by genetic collagen overproduction, whereas a keloid stems from rapid stretching. — This statement transposes the causes; blowouts are mechanical injuries and keloids are genetic.
• A blowout forms exclusively on the front of the earlobe, while a keloid forms on the back. — Blowouts typically protrude from the back of the lobe, and keloid placement is not restricted by ear surface side.
7. Which set of clinical signs points to a true bacterial infection rather than an isolated mechanical blowout?
• A firm, pink ring of tissue behind the lobe without heat or fever. — A firm, pink ring without heat is characteristic of an uncomplicated mechanical blowout.
• Clear fluid weeping with mild tenderness immediately following a dead stretch. — Minor serous fluid and mild tenderness right after stretching reflect minor mechanical irritation rather than infection.
✓ Radiating heat, throbbing pain, and yellow or green discharge with a foul odor. — Infections are defined by classic infectious symptoms, including localized heat, severe throbbing pain, and purulent, foul-smelling discharge.
• A donut-shaped ridge of soft tissue that has remained unchanged for three months. — A long-standing, painless ridge indicates chronic scar tissue from a previous blowout.
8. What is the appropriate long-term management strategy for a chronic, fully healed blowout scar?
• Forcefully push the raised tissue back into the piercing channel using a taper. — Extruded tissue cannot be manually pushed back into place once scar tissue has fully formed.
✓ Perform daily massages with vitamin E oil or Bio-Oil once the skin is fully healed. — Gentle daily massage on intact, healed skin helps break down mature collagen buildup over several months.
• Apply topical antibiotics twice daily until the raised tissue flattens. — Antibiotics have no mechanism for breaking down non-infected, mature scar tissue.
• Immediately stretch to a larger gauge to smooth out the raised ring. — Increasing gauge size adds pressure, which aggravates tissue displacement and worsens scarring.
9. Why is acrylic considered an unsafe material for stretching body piercings?
• It is too heavy and causes gravitational tearing of the lower earlobe. — Acrylic is lightweight; its primary dangers relate to surface friction, porosity, and heat sensitivity.
✓ It is porous, cannot be autoclaved, and possesses high surface friction that causes micro-tears. — High surface friction pulls on healing tissue during insertion, while porosity prevents proper sterilization.
• It breaks down into toxic liquids when exposed to standard 0.9% saline spray. — Saline spray does not dissolve or liquify acrylic jewelry.
• It induces immediate keloid formation regardless of the user's genetic predisposition. — Keloids require a genetic predisposition and are not automatically triggered by material type alone.
10. If a client experiences sharp pain or significant resistance during a stretch, what action should be taken immediately?
• Push through the pain quickly to finish the insertion before swelling begins. — Forcing jewelry through resistance tears the fistula lining and directly causes blowouts.
• Apply tea tree oil to lubricate the canal and force the plug into place. — Harsh oils irritate open tissue, and forcing jewelry causes mechanical tears.
✓ Stop, remove the jewelry, downsize to the previous gauge, and wait at least two weeks. — Stopping and downsizing immediately relieves mechanical stress, preventing tears and allowing the fistula to rest.
• Switch immediately to an acrylic taper of the same target diameter. — Switching to acrylic tapers maintains excessive force while introducing high friction and unsterile materials.
Extended Reference Table
8 of 8 rows
Extended reference table generated from the article and its verified research sources. Bracketed numbers jump to the matching entry in the Technical References below.
Safety
Item or Practice
Category
Material Specifications
Compliance or Standards
Clinical Application or Description
Safety or Health Notes
Source
✅
Lobuloplasty (Earlobe Repair)
Surgical Procedure
Fine sutures (6-0 or smaller) for layered closure of soft tissue (fatty tissue).
GMC Specialist Register, RACS standards
A minor surgical procedure to address torn, stretched, or damaged earlobes by removing scar tissue and suturing healthy edges.
Performed under local anaesthesia; risks include infection, haematoma, and keloids. Required if stretching exceeds 10mm or for severe blowouts.
Print-ready reference posters for your studio or your own wall. Free to download and display, embed on your own site with attribution. Click any poster to preview it full size before downloading.
[2]ASTM F136 - Standard Specification for Wrought Titanium-6Aluminum-4Vanadium ELI Alloy for Surgical Implant Applications standard catalogue
[3]Winter GD. Formation of the scab and the rate of epithelization of superficial wounds. Nature. 1962;193:293-294 [doi:10.1038/193293a0](https://doi.org/10.1038/193293a0)
[4]Association of Professional Piercers. "Stretching your Piercing" brochure, print-quality PDF (2017 edition, current on the APP Stretching page). safepiercing.org
[5]Braverman IM. The cutaneous microcirculation. J Investig Dermatol Symp Proc. 2000;5(1):3-9. [PMID 11147672](https://pubmed.ncbi.nlm.nih.gov/11147672/)
[6]Association of Professional Piercers, Stretching Your Piercing, safe stretching guidelines. safepiercing.org/stretching
[7]Iftekhar N, Rahman M, Ahmed M. The history and current trends of earlobe stretching. Dermatology. 2021;237(2):303-305. PMID 31991419.
[8]Conte C, et al. Complications of body piercings: a systematic review. Cutis. 2023;112(3):139-145. PMID 37903388.
Chief Engineer, Poli International · Creator of BioFlex® body jewelry
Patrick has spent 25+ years manufacturing body jewellery and studio equipment, and is the creator of BioFlex® body jewelry. He created the push-fit system so jewellery separates on impact instead of tearing the piercing. He also ran 10 to 25 minute consultations before piercing, and treats aftercare as a standing invitation rather than a leaflet.