
Cartilage piercings hurt more than soft-tissue piercings because cartilage is avascular: it has no blood supply of its own, heals by diffusion rather than direct vascular repair, and takes 6 to 12 months to fully stabilise. Helix and conch are both cartilage piercings, but they differ in thickness, nerve proximity, and healing behaviour. Here is what to expect from each, and why the difference matters.
If you are planning your first ear cartilage piercing, the question is usually "helix or conch?" The helix is the classic: the outer rim of the ear, visible from the front and side, the piercing everyone recognises. The conch is the centre: the deep bowl of the ear, more hidden but more dramatic when it heals. Both go through cartilage. Both hurt more than a lobe. But they hurt differently, heal differently, and suit different jewellery goals. Knowing the difference before the needle goes in means you make the right choice the first time.
What makes cartilage piercings different from soft tissue
Cartilage is not like skin. It has no blood vessels, no lymphatics, and no direct nerve supply of its own. Every chondrocyte (cartilage cell) survives by diffusion: nutrients and oxygen seep in from the perichondrium, the thin fibrous membrane wrapped around the cartilage surface. When a needle passes through cartilage, it does not cut a clean channel: it crushes the avascular matrix, creating a zone of mechanical injury around the puncture site that cannot be repaired by the body's normal vascular wound-healing cascade.
A lobe piercing, by contrast, passes through well-vascularised fibro-adipose tissue. Blood arrives within seconds, platelets form a plug, fibroblasts migrate in, and collagen deposition begins within days. The lobe is soft, mobile, and forgiving. The cartilage is rigid, diffusion-dependent, and slow. This is why a lobe piercing can feel stable in 4 to 6 weeks, while a cartilage piercing may still be tender at 6 months. The biological difference is not subtle, and it explains every practical difference in pain, healing, and aftercare between the two categories.
Cartilage thickness varies by ear region. The helix is typically 0.8 to 1.5 mm thick at the outer rim, tapering toward the upper curl. The conch is substantially thicker, 2.0 to 3.5 mm in the deep central bowl, depending on individual anatomy. Thicker cartilage means a longer needle transit time, a larger zone of mechanical injury, and more diffusion-dependent tissue to remodel. This is the primary reason the conch hurts more than the helix: not nerve density, but simple tissue thickness and the physics of the needle passing through it.
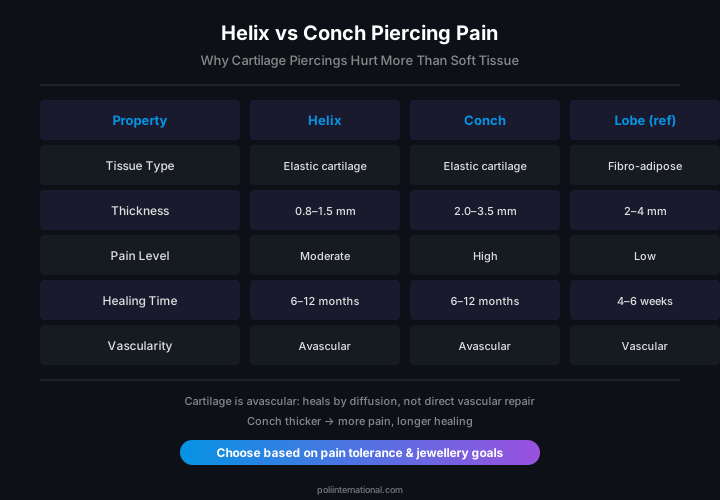
Key differences at a glance
| Property | Helix Piercing | Conch Piercing | Lobe (soft tissue, for reference) |
|---|---|---|---|
| Tissue type | Elastic cartilage, outer rim | Elastic cartilage, central bowl | Fibro-adipose soft tissue |
| Cartilage thickness | 0.8-1.5 mm | 2.0-3.5 mm | No cartilage |
| Blood supply | Diffusion via perichondrium only | Diffusion via perichondrium only | Direct capillary network |
| Needle sensation | Sharp, brief pressure point | Deeper pressure, audible crunch in some cases | Quick pinch, minimal pressure |
| Typical pain rating (1-10) | 4-6 | 6-7 | 2-3 |
| Initial healing window | 6-9 months | 6-12 months | 4-8 weeks |
| Swelling window | Days 2-5, mild to moderate | Days 2-7, moderate | Days 1-3, mild |
| Sleep disruption | Unilateral sleep required 4-6 weeks | Unilateral sleep required 6-12 weeks minimum | Minimal after week 1 |
| Jewellery type (initial) | Straight labret stud, 16g or 18g | Straight labret stud, 14g or 16g | Straight barbell or labret, 18g or 20g |
| Ring/hoop suitable initially? | No: curvature creates pressure on straight channel | No: ring movement disturbs fistula formation | Rings acceptable in some cases |
| Rejection risk | Low (cartilage anchors well) | Very low (deep placement) | Very low |
| Perichondritis risk | Moderate if aftercare is poor | Moderate: deeper placement = longer contamination window | Essentially zero |
| Migration risk | Low with correct angle | Very low: conch bowl is anatomically stabilised | Low |
What a helix piercing feels like
The helix piercing needle passes through the outer rim of the ear, entering through the anterior surface and exiting the posterior edge. The cartilage here is relatively thin and the needle transit is fast. Most clients describe the sensation as a sharp, localised pressure that peaks for about one second, followed by a dull warmth as blood flow returns to the surrounding perichondrium. The sharpness comes from the needle piercing the perichondrium itself, which IS innervated. The cartilage beneath has no nerve endings, so the deeper transit feels like pressure rather than pain.
After the jewellery is inserted, the helix typically settles into a low-grade ache that persists for 24 to 48 hours. This is perichondrial inflammation: the membrane's vascular response to injury, not cartilage pain. Swelling peaks around day 3 and gradually subsides over the following week. The helix is exposed: it sits on the outermost edge of the ear where it catches on hair, masks, headphones, and pillowcases. Accidental snagging is the most common cause of prolonged helix healing, and each snag re-injures the forming fistula, restarting the inflammatory cycle. A helix that would heal in 6 months undisturbed can take 12 months with repeated trauma.
Because the helix is on the ear rim, sleeping on the pierced side is the single most disruptive variable. Even a travel pillow with a centre hole does not fully eliminate pressure on the outer rim. Clients who sleep on their side should plan for 4 to 6 weeks of modified sleep position, and ideally wait until the piercing is fully stable (6+ months) before sleeping directly on it without protection.
What a conch piercing feels like
The conch needle passes through the thickest cartilage in the ear, entering through the anterior bowl and exiting through the posterior surface behind the ear. The transit is noticeably longer than a helix: the needle must travel through 2 to 3.5 mm of dense avascular cartilage compared to the helix's 1 mm or less. Because the conch bowl is concave, the piercer must stabilise the ear with a receiving tube placed behind it, and the client will feel firm pressure against the back of the ear before the needle enters.
The sensation is often described as a deep, dull pressure with a sharp entry point, accompanied in some cases by an audible "crunch" or "pop" as the needle penetrates the dense cartilage plate. This sound is normal and harmless: it is the needle tip breaking through the cartilage matrix, not bone or any structure that carries risk. It can be startling if unexpected, but it does not indicate a complication.
After the jewellery is in place, the conch tends to ache more deeply than the helix and for longer: 3 to 5 days of dull throbbing is typical, especially when the ear warms up at night (vasodilation increases pressure in the enclosed inflammatory environment). The conch's deep placement means it is less exposed to external snagging than the helix: hair, masks, and headphones rarely touch it directly. This is a significant healing advantage. However, the conch is closer to the ear canal, so build-up of dried exudate behind the jewellery is harder to see and clean without a mirror. Meticulous saline irrigation is essential during the first 6 weeks to prevent debris accumulation in the concave bowl.
Sleeping on a healing conch is difficult. The ear's central position means that any pressure on the side of the head transfers directly to the piercing site. A travel pillow is more effective for a conch than a helix because the conch sits inside the hole rather than on the rim, but the inflammatory ache may still wake light sleepers. Plan for 8 to 12 weeks of strictly unilateral sleep, longer than the helix requirement.
Why cartilage healing pain lasts for months
The pain of a cartilage piercing does not end when the initial swelling subsides. Clients routinely report tenderness when the piercing is touched, even months after the procedure. This is not a sign of infection or failure: it is normal avascular healing behaviour. Because cartilage has no blood supply, the body must remodel the injury zone entirely through diffusion-driven processes. Fibroblasts migrate into the perichondrium and slowly deposit collagen around the jewellery, forming a fistula: a tube of scar tissue that lines the piercing channel. This process takes 6 to 12 months.
During that window, the fistula is fragile. Any mechanical disturbance: snagging, pressure, jewellery changes, even aggressive cleaning, disrupts the immature collagen matrix and reinitiates the inflammatory cascade. The piercing that "felt fine last week but hurts again today" is almost always a fistula that was accidentally disturbed, not an infection. The process is frustrating but predictable. Understanding it reduces the anxiety that drives unnecessary jewellery removal and aftercare escalation.
Cartilage piercings also carry a specific infection risk that soft tissue piercings do not: perichondritis, infection of the perichondrial membrane. Because the cartilage itself has no blood supply, systemic antibiotics delivered through the bloodstream cannot reach an infection inside the cartilage matrix. Perichondritis requires aggressive, early antibiotic treatment, typically fluoroquinolones (e.g., ciprofloxacin) which penetrate avascular tissue better than standard beta-lactams. Signs include spreading redness beyond the immediate piercing site, warmth extending along the ear contour, throbbing pain that worsens rather than improves after day 5, and, in advanced cases, deformity of the ear contour (cauliflower ear). Any of these signs warrants immediate medical attention, not home treatment.
Pain management: what helps and what makes it worse
What helps
- Ice (indirect): A cold pack wrapped in a clean cloth, applied to the area around the piercing (not directly on it) for 10 minutes at a time, reduces perichondrial swelling and dulls the ache. Do this during the first 48 hours.
- Sterile saline irrigation: Twice-daily rinsing with 0.9% sterile saline removes dried exudate without the mechanical irritation of cotton buds or wipes. Irrigation, not scrubbing.
- Ibuprofen (if medically appropriate): 400 mg of ibuprofen reduces perichondrial inflammation and provides analgesia. Take with food. Do not take before the procedure (it mildly inhibits platelet function). Paracetamol is the safer pre-procedure option.
- Travel pillow: A firm memory-foam travel pillow with the pierced ear positioned in the centre hole allows side-sleeping without direct pressure. More effective for conch piercings than helix, but helpful for both.
- Downsize on schedule: After the initial swelling subsides (4 to 8 weeks for helix, 6 to 10 weeks for conch), have your piercer downsize the post to a shorter length. Excess post length creates a lever arm that amplifies every accidental touch into fistula-disturbing force. Downsizing is not optional: it is a healing intervention.
What makes it worse
- Sleeping on it: Direct pressure on a healing cartilage piercing is the most common cause of prolonged pain, irritation bumps, and migration. No exceptions.
- Twisting or rotating the jewellery: The old advice to "turn the earring so it doesn't stick" is wrong. Rotating jewellery in a healing fistula tears the immature collagen matrix and introduces surface bacteria into the wound track. Leave it alone.
- Tea tree oil, alcohol, hydrogen peroxide: These are irritants, not antiseptics suitable for healing piercings. They dry the perichondrium, delay epithelialisation, and can cause chemical burns on healing tissue. Sterile saline only.
- Changing jewellery too early: Removing and reinserting jewellery before the fistula is epithelialised (minimum 4 to 6 months, ideally 6+) causes the channel to collapse and reform around the new jewellery, restarting healing.
- Over-ear headphones: Direct pressure on a healing helix or conch from headphone pads. Use in-ear monitors or bone-conduction headphones during the healing period.
Key takeaways
- Cartilage piercings hurt more and heal slower than lobe piercings because cartilage is avascular: no blood supply, healing by diffusion only.
- The conch hurts more than the helix because the cartilage is 2 to 4 times thicker, meaning a longer needle transit and a larger injury zone.
- Both piercings require 6 to 12 months for full fistula maturation. Tenderness at 4 months is normal, not a sign of failure.
- The helix is more exposed to external snagging (hair, masks, headphones); the conch is more protected but harder to clean and more disruptive to sleep.
- Never twist, rotate, or change jewellery during healing. Irrigate with sterile saline only. Downsize on schedule.
- Perichondritis is a medical emergency: spreading redness, worsening pain after day 5, and ear contour changes require immediate antibiotic treatment.
Frequently asked questions
Q: Which hurts more: a helix or a conch piercing?
The conch hurts more than the helix for most people. The conch cartilage is 2 to 4 times thicker (2.0 to 3.5 mm vs 0.8 to 1.5 mm for the helix), so the needle transit takes longer and creates a larger injury zone. Both are cartilage piercings, so both are more painful than a lobe, but within cartilage placements the conch ranks higher on most piercer pain scales. Individual pain perception varies with piercer technique, needle gauge, and personal threshold: a fast, skilled piercer with a 16g needle will produce less discomfort than a slow insertion with a 14g needle, regardless of placement.
Q: How long does a helix or conch piercing hurt after the procedure?
The sharp pain of the needle itself lasts about one second for a helix and two to three seconds for a conch. After that, both settle into a dull ache that typically lasts 24 to 72 hours for a helix and 3 to 5 days for a conch. Tenderness to touch can persist for months as the fistula matures: this is normal avascular healing behaviour and does not indicate a problem. If pain worsens after day 5, or spreads beyond the immediate piercing site with redness and warmth, seek medical evaluation for possible perichondritis.
Q: Can I get both a helix and a conch piercing in the same session?
Yes, but on the same ear only if you are prepared for amplified swelling and a longer, more uncomfortable initial healing period. Two cartilage piercings on the same ear mean the entire ear will swell significantly, and the inflammatory response from one site will affect the other. Many piercers recommend spacing cartilage piercings on the same ear by at least 4 to 6 weeks, or doing one on each ear in the same session (allowing you to sleep on the non-pierced side while both heal). If you do both on the same ear, expect 5 to 7 days of significant swelling and plan for strictly unilateral sleep for 8 to 12 weeks minimum.
Q: Why does my healed helix piercing still hurt sometimes?
A cartilage piercing that is technically "healed" (epithelialised fistula, no active wound) can still be tender for up to 18 months after the procedure. The fistula is scar tissue, not original anatomy: it has less flexibility, different nerve distribution, and responds to pressure or temperature changes differently than intact skin. Sleeping on it, wearing over-ear headphones, or changing to jewellery with a different gauge or curvature can all trigger tenderness in an otherwise stable piercing. This does not mean it is infected or rejecting. It means the fistula is still remodelling. If the tenderness is persistent and accompanied by a bump, see your piercer for a fit assessment: post length, jewellery material, or angle may need adjustment.
Also compare
- Piercing pain guide: pain profiles for 20+ piercing placements - Healing tracker: personalised healing timeline for your piercing - Piercing angle guide: why needle angle determines healing success - Piercing migration risk: assess rejection risk by placement - Reaction triage wizard: is it healing, irritated, or infected? - Client health screening: medical clearance for piercings - Wound healing biology: the science of fistula formation - Anthropometry and jewellery sizing: skin tension and placement science - Ear cartilage piercing: healing, migration, and rejection - Least painful piercings for first-timers - Piercing jewellery change timing guide6. Conch vs Helix Piercing: Pain, Healing, and What to Expect
The query 'conch piercing vs helix' usually comes down to three practical questions: which one hurts more, which heals faster, and which fits your anatomy and lifestyle. Here is the direct comparison.
Pain location and intensity. Helix piercings sit on the upper outer cartilage rim. The pain is sharp and immediate because the needle passes through dense avascular cartilage, but it fades quickly. Conch piercings go through the deep bowl of the ear, the thickest cartilage in the ear. The initial pain is often described as more pressure than sharpness, and it can throb for longer because the tissue is thicker and has even less blood supply. Neither is a soft-tissue piercing, so do not expect lobe-level discomfort.
Healing times. Both are cartilage piercings and both heal by diffusion, not direct vascular repair. Expect 6 to 12 months for full healing. The conch often feels healed earlier because it is protected inside the ear bowl, but the helix is more exposed to hair, helmets, and pillow friction. In practice, helix piercings get irritated more often during healing, which can stretch the timeline.
Which hurts more? There is no universal answer, but the pattern is consistent: helix pain is sharper and shorter; conch pain is deeper and throbs longer. If you are deciding between the two, pick based on anatomy and aftercare discipline, not fear of the needle.
I have been making body jewellery for 25 years, and the single biggest factor in how a cartilage piercing feels and heals is not the placement, it is what you put in it. Properly fitted, lightweight jewellery that moves with the tissue reduces pressure on the healing channel. That is exactly why I developed BioFlex® in medical-grade PP-R polymer: it is strong, non-metallic, and kind to fresh cartilage.
Practical takeaway. Whichever you choose, get the placement assessed by a professional piercer, avoid sleeping on that side, and do not skip downsizing. If you want to understand the jewellery side of cartilage healing in more detail, read our guide to piercing aftercare and jewellery materials.


