
Ear Cartilage Piercings: Heal, Migrate, and Reject Differently Than You Think
Key Takeaways:
» Cartilage is avascular (no internal blood supply); all nutrient and immune transport happens via the perichondrium membrane, making healing measured in months instead of weeks
» Different placements carry wildly different biomechanical loads: an industrial barbell couples two holes into a rigid torque lever, while a daith sits protected inside the ear's acoustic shadow
» Migration jewelry sizing science is not rejection; a migrating cartilage fistula walls itself off, while a rejecting one extrudes the jewelry under pressure necrosis with perichondritis risk
» Material and geometry matter more in cartilage than anywhere else: rigid bars, point contact, and snag torque are primary drivers of failure
1. Cartilage Is Not Lobe: The Avascular Problem
The earlobe is soft, well-perfused fibro-fatty tissue that heals in weeks. Cartilage is the opposite: elastic and hyaline cartilage in the ear has almost no intrinsic blood supply. It is avascular. Chondrocytes (cartilage cells) survive via diffusion from the perichondrium, a dense connective tissue membrane carrying the microvascular network the cartilage itself lacks. When a needle passes through the perichondrium and cartilage, it severs those diffusion pathways. The puncture site becomes ischaemic until the perichondrium repairs and re-establishes the diffusion gradient.
This is why cartilage piercings are slow. A lobe fistula may be structurally stable in 8 weeks; a helix or conch fistula is still immature at 12 weeks and not fully biomechanically stable until 6 to 9 months. During that window, any sustained mechanical load (side-sleeping, a poorly fitted bar, snagging) disrupts the fragile perichondrial repair and triggers the inflammatory cascade.
The infection risk is also fundamentally different. Because cartilage has no internal blood supply, systemic antibiotics struggle to reach an infection seeded into the cartilage itself. Perichondritis, infection of the perichondrium, is a medical emergency that can cause cartilage necrosis and permanent ear deformity if not treated aggressively.
2. Placement Mechanics: Why an Industrial Is Nothing Like a Daith
Not all cartilage piercings are biomechanically equal.
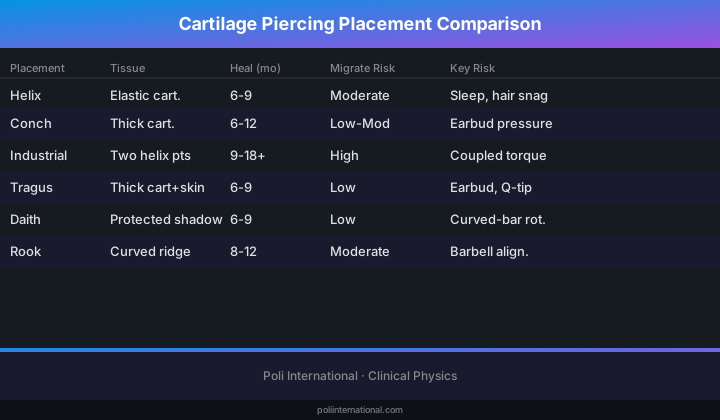
The ear is a complex surface with dramatically different loading environments:
| Placement | Tissue Type | Healing (months) | Migration Risk | Key Mechanical Risk |
|---|---|---|---|---|
| Helix | Elastic cartilage, thin | 6-9 | Moderate | Sleep compression, hair snag |
| Conch | Thick cartilage plate | 6-12 | Low-Moderate | Earbud/headphone pressure |
| Industrial | Two helix points, rigid bar | 9-18+ | High | Coupled torque, differential swelling |
| Tragus | Thick cartilage + skin flap | 6-9 | Low | Earbud displacement, Q-tip trauma |
| Daith | Protected acoustic shadow | 6-9 | Low | Curved-bar rotation in tight bend |
| Rook | Curved ridge, double curve | 8-12 | Moderate | Curved barbell alignment stress |
The industrial (scaffold) piercing is the most mechanically unforgiving. It connects two separate helix piercings with a single rigid barbell, creating a coupled system: any force on one hole transmits torque directly to the other. If the two piercings were not aligned perfectly, or if differential swelling tilts one hole during healing, the barbell acts as a constant-stress lever. The result is persistent inflammation, pressure necrosis, and one of the highest migration rates in body piercing.
By contrast, the daith sits deep inside the ear's concha, protected from direct pillow contact and hair snag by the acoustic shadow of the outer ear. Its main risk is curved-barbell rotation if the jewelry is too short or too heavy, deforming the fistula into an oval cross-section over time.
3. Migration vs Rejection: What Is Actually Happening Under the Skin
These two words are used interchangeably online and in studios. They are different processes with different physics and outcomes.
Migration is a fistula shifting position. As granulation tissue remodels into mature scar, asymmetric loading (sleeping consistently on one side, wearing a bar that is too long) pulls the fistula through the tissue plane. The body walls it off with a new epithelial lining as it moves. A migrated piercing sits at a visible angle or closer to the edge, but remains a viable, lined channel. Common in industrials where one hole drifts, and in helix piercings placed too close to the rim.
Rejection is extrusion. Sustained lateral load causes pressure necrosis of the cartilage and perichondrium directly in front of the jewelry. The body resorbs necrotic tissue rather than repairing it, and the jewelry migrates outward, toward the skin surface. The fistula opens up rather than walls off. The visible sign is a thinning bridge of tissue between entry and exit points, often with a pink or translucent line where the jewelry shows through the skin. This is irreversible.
The mechanism: cartilage under sustained compression above roughly 32 mmHg (capillary closing pressure) becomes ischaemic. Chondrocytes die. The perichondrium separates. The body treats the dead tissue as debris and resorbs it, advancing the jewelry outward, the same pressure-ulcer mechanism that causes bedsores.
Lumping migration and rejection together causes people to remove piercings that were merely shifting and could have stabilised with a simple jewelry change. For the difference between irritation bumps and true rejection in soft-tissue piercings, see our deep dive on TikTok rejection panic.
4. Patrick's Note: What 20 Years of Watching Cartilage Failures Taught Me
I have seen more cartilage disasters than I care to count, and they share a few avoidable causes. The single biggest driver of failure is not the piercer's technique or the aftercare routine: it is the jewelry left in for the full healing period.
Most studios pierce with a longer bar to accommodate swelling. Correct. The mistake is leaving that longer bar in for 6 to 12 months. After swelling subsides at 4 to 6 weeks, that extra length becomes a lever arm. Every time the wearer sleeps on it, the pillow pushes the long bar laterally, transmitting torque through the fistula. Repeated micro-trauma keeps the perichondrium in a chronic inflammatory state. Downsizing to a well-fitted shorter bar at 4 to 8 weeks is the single highest-impact intervention for cartilage healing. I have seen perfectly placed piercings fail solely because no one mentioned downsizing.
Material matters more in cartilage than in soft tissue. A rigid titanium or steel barbell transmits 100% of any pillow force directly into the cartilage. A lower-modulus material like BioFlex (medical-grade PP-R copolymer) absorbs displacement energy through elastic deformation, reducing peak contact stress on the fistula walls. A rigid bar under sustained lateral load in avascular tissue is a pressure-ulcer recipe. We covered the full biomechanics argument in flexible vs rigid body jewelry, and the material case for BioFlex in initial piercings and the right material.
I have seen perfectly placed industrials fail at month 14 because the rigid barbell kept both fistulas in constant low-grade tension. Remove the bar, let each hole heal independently with separate jewelry for 3 to 4 months, then re-introduce the single bar, and it works. The cartilage needs independence before it can handle coupling. It is physics.
5. FAQ: Cartilage Piercing Realities
Q: My helix is 4 months old and still gets angry when I sleep on it. Is it failing?
Almost certainly not. Cartilage takes 6 to 9 months minimum to reach biomechanical maturity, and some people take 12 to 18. "Angry" (red, slightly swollen, a small irritation bump) after sleeping on it means the perichondrium is still remodelling and you compressed the fistula. It is not failing: it is telling you to stop sleeping on it. Use a travel pillow (ear in the hole) and downsize if you have not already.
Q: How do I know if my industrial is migrating vs rejecting?
Migration: holes shift sideways but the tissue bridge between them is thick and opaque. The piercing looks off-angle but no jewelry is visible through the skin. This can stabilise with separate jewelry and time. Rejection: the tissue bridge thins, becomes translucent or pink, and you can see the bar outline through the skin. Rejection progresses toward the surface; migration progresses sideways. Migration can stabilise. Rejection cannot. Remove immediately if you see translucency.
Q: Can I put BioFlex in a fresh cartilage piercing?
Yes. BioFlex is engineered as an initial-piercing material and is ISO 10993 biocompatibility tested. Its lower elastic modulus absorbs displacement rather than transmitting it to the fistula wall. For cartilage specifically, this reduces peak contact stress during healing, which is clinically relevant because cartilage has no internal blood supply. However, a BioFlex bar that is too long still acts as a lever arm regardless of material flexibility. Downsize at the same 4 to 8 week point.
Conclusion
Cartilage piercings fail for reasons that are predictable, mechanical, and almost entirely avoidable. The avascular nature of cartilage means healing is measured in months, not weeks: diffusion is slow, not broken. Placement dictates the loading environment; an industrial is a coupled rigid system that amplifies every force, while a daith is mechanically protected by the ear's geometry. Migration and rejection are different processes with different endpoints, and distinguishing them saves piercings that can be saved. Material selection, bar length management, and sleep discipline are the primary variables. A quiet ear heals. A compressed one does not.
6. Can Cartilage Piercings Migrate or Reject? What Actually Decides
Short answer: yes, and more often than most piercers admit. The longer answer is that migration and rejection are not the same event, they do not happen at the same rate across placements, and the difference between them comes down to tissue geometry.
Migration is movement. The jewellery shifts through the tissue, gradually changing angle or position, and the piercing may still survive if you catch it. Rejection is the endpoint — the body has decided the jewellery is a foreign object with no viable channel around it, and extrudes it out through the skin. A migrated piercing that nobody intervenes on usually becomes a rejected piercing. That is why I tell clients to photograph a new cartilage piercing every two weeks: the only reliable way to detect migration is comparison over time, not a single look in the mirror.
For short answer queries: are bridge piercings permanent? A bridge piercing sits in very thin, highly mobile tissue between the eyes, so it is notoriously prone to migration and rejection and cannot be described as permanent. A well-healed daith or lobe piercing is far more stable. Can lobe piercings migrate? Yes, though less dramatically — lobes are soft tissue with good blood supply, so they tend to heal well but can "cheese-wire" downward under heavy or poorly supported jewellery over years.
Cartilage is a different problem entirely. It is avascular — no internal blood supply — so all nutrient and immune transport runs through the perichondrium membrane on the surface. That single fact explains almost everything: why healing is measured in months, not weeks, and why any irritation, pressure or infection at the site has a much narrower margin before the body gives up and starts extruding. Cartilage rim piercings such as helix and industrial sit in thin, curved sections of the rim; industrials also connect two puncture sites with one rigid bar, and any change in angle at either end loads the channel asymmetrically. That is why industrials migrate more than daiths: more leverage, longer channel, two wound sites instead of one.
In my twenty-five years making BioFlex®, I have seen exactly one pattern repeat: the piercings that reject are the ones that were never given a stable, low-pressure channel in the first place. Correct angle, correct length for swelling, and jewellery that does not add mechanical stress are the three variables you actually control. If you want to understand how initial jewellery choice and aftercare interact with the healing timeline, start with our guide to piercing aftercare at /blog/piercing-aftercare-guide/, and use the sizing and placement tools at /tools/ before your next appointment.
6. Do All Cartilage Piercings Reject — and Which Placements Are Most at Risk?
Not every cartilage piercing rejects, but some placements are far more prone to migration and extrusion than others. The deciding factors are tissue thickness, mechanical stress, and how much skin the jewellery passes through. Thin, high-curvature areas — the cartilage rim, helix edge, and bridge — have less tissue to anchor the channel, so a poorly fitted or too-heavy piece can slowly cut its way out. This is why "cartilage rim piercing" queries almost always return rejection warnings: the rim simply doesn't offer the depth that a conch or daith does.
A bridge piercing is a surface piercing, not a cartilage piercing in the classic sense, and that distinction matters. It sits in the loose tissue above the nose bridge where there is no cartilage to grip the jewellery at all. A bridge is not permanent by nature — it is a long-term temporary piercing that survives only as long as the tissue around the channel holds. If you want to know whether a bridge will last, the honest answer is: it can, for years, but it is never guaranteed the way a lobe or a healed conch is.
Can lobe piercings migrate? Yes — and this surprises people who assume lobes are foolproof. A lobe that was pierced at an angle, stretched too fast, or loaded with heavy jewellery can migrate downward or forward over time. The mechanism is identical to cartilage migration: continuous pressure against living tissue causes the body to remodel around the foreign object. The difference is that lobes have blood supply, so they heal faster and tolerate correction better. Cartilage does not — it is avascular, and every millimetre of migration is permanent unless you retire the piercing.
In my twenty-five years making BioFlex®, I have seen more rejection cases caused by jewellery than by anatomy. Too-heavy ends, wrong bar length, cheap metal that triggers inflammation — all of these load the channel and accelerate extrusion. For cartilage, I strongly advise BioFlex® PP-R polymer: it is flexible, medical-grade, certified as passing the ISO 10993 biological tests and built on USP Class VI resin, and it does not carry the weight or the allergic risk that stainless steel and titanium can. People wear it for years without issue. If you are fighting a migrating piercing, the first variable to change is the jewellery, not your aftercare.
If you want to check whether your current jewellery is helping or hurting, run your measurements through our piercing jewellery size and material tool before you buy anything else.
6. Can Lobe Piercings Migrate and Are Cartilage Piercings Permanent?
Most people assume migration is a problem exclusive to cartilage. It isn't. A lobe piercing can migrate too, and the mechanism is identical — the jewellery applies continuous pressure to tissue that cannot accommodate it, and the body gradually widens the channel in the direction of least resistance. The difference is that lobes are vascular, so a migrating lobe piercing is often painless and easy to miss until the jewellery suddenly sits several millimetres from where it was placed. Cartilage, being avascular, gives you earlier warning signs: persistent redness, a thinning bridge of skin over the bar, and a change in the angle of the exit hole. If you can see more of the barbell than you could a month ago, that is not your imagination. That is migration in progress.
I have been making BioFlex® PP-R jewellery for 25 years, and I will tell you plainly: the single most common cause of migration I see is not rejection, it is mechanical load. A ring that is too tight, a barbell that is too short, a stud that gets slept on every night — all of these transfer force to the tissue. Cartilage does not forgive that. The perichondrium can only remodel so much before it starts to give way.
So are cartilage piercings permanent? Yes — if they heal. A fully healed cartilage piercing with appropriate jewellery and no chronic pressure is as permanent as any other piercing. But 'permanent' is conditional. Placement decides the odds: a well-placed helix or tragus with a properly fitted bar has a far better long-term prognosis than a superficial rim piercing or a poorly angled industrial. If your piercer cannot explain the anatomy behind the placement, that is your signal to ask more questions before the needle goes in.
What about rejection specifically? True rejection — where the body actively extrudes the jewellery — is rarer than migration, but it is more serious. It happens when the immune system identifies the jewellery as a foreign body it cannot isolate. Signs include the jewellery becoming visible through the skin, a change in colour or texture around the site, and a persistent discharge that is not lymph. If you see the bar through the skin, stop waiting. Remove the jewellery and let the tissue recover. Re-piercing through scar tissue is possible, but it requires a different placement strategy and a longer healing window.
The practical takeaway: migration is mechanical, rejection is immunological, and both are manageable if you catch them early. Check your jewellery fit monthly. Photograph the site so you can compare. And if you are unsure whether what you are seeing is normal healing or early migration, use our piercing troubleshooting tool to walk through the signs step by step before you make any changes.


