
The three skin layers and why each matters
Key Takeaways:
» Tattoo pigment must reach the papillary-to-upper reticular dermis; epidermal deposition sheds in 4-6 weeks, hypodermal deposition causes permanent blowout
» Dermal thickness varies 8-fold across the body, from 0.5 mm at the eyelid to 4.0 mm at the upper back; needle depth must be calibrated to the site
» Six millimetres of tissue depth is the minimum for piercing stability; measure with calipers, not by eye
» Cartilage piercings take 2-4 times longer to heal because cartilage is avascular and heals by diffusion
» Ageing dermis loses roughly 1% of collagen per year from age 30, narrowing the safe depth window for tattooing
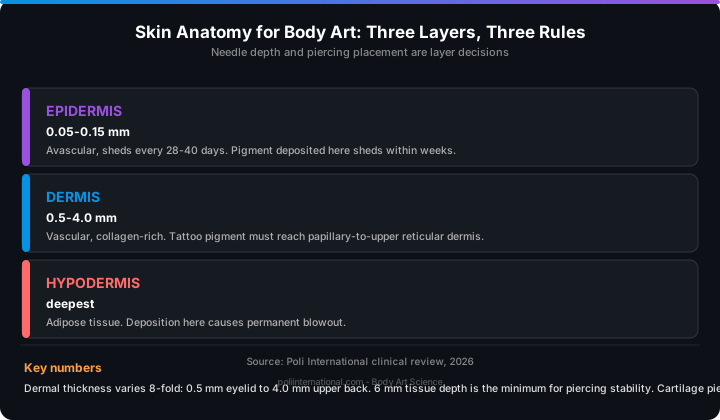
1. The three skin layers
Human skin is a stratified organ with three distinct layers. From surface to depth: the epidermis (outermost, avascular, continuously shedding), the dermis (middle, vascular, structural, collagen-rich), and the hypodermis (deepest, primarily adipose tissue with loose connective tissue). Each layer behaves differently under a needle, heals differently, and determines whether a body art procedure succeeds or fails.
| Layer | Typical thickness | Key features | Body art relevance |
|---|---|---|---|
| Epidermis | 0.05-0.15 mm (0.5 mm on palms/soles) | Avascular, stratified squamous epithelium, 28-40 day turnover cycle | Pigment deposited here is shed within weeks; epidermal-only wounds heal without scarring |
| Dermis | 0.5-4.0 mm (varies by body site) | Vascular, collagen-dominant ECM, contains fibroblasts, macrophages, nerve endings | Target layer for tattooing; piercing fistula forms here; thickness determines jewellery length and migration resistance |
| Hypodermis | Variable (mm to cm) | Adipose-dominant, loose areolar connective tissue, large blood vessels | Pigment deposited here disperses (blowout); piercings with insufficient dermal capture migrate |
2. Epidermis: the surface that heals first
The epidermis is 0.05 to 0.15 mm on most body sites and up to 0.5 mm on palms and soles. It has no blood supply; oxygen and nutrients reach it by diffusion from the dermal capillary bed below. An epidermal-only wound does not bleed and heals by simple epithelial migration.
For body art, the epidermis matters in three ways. First, the shedding problem: if tattoo pigment is deposited only in the epidermis, keratinocytes migrating upward over 28-40 days carry it to the surface where it exfoliates. This is why a shallow tattoo fades to near-invisibility within 4-6 weeks. Second, the epidermal seal after piercing: epithelial cells migrate centripetally around the jewellery post, forming a tight seal within 48-72 hours. Disrupting this seal by rotating jewellery or changing it prematurely reopens the channel to contamination. Third, epidermal thickness and pain perception: the epidermis itself has no nerve endings, so pain from tattooing and piercing only begins when the needle reaches the dermis.
3. Dermis: where the work actually happens
The dermis divides into two sub-layers: the papillary dermis (superficial, 0.3-0.5 mm thick, high capillary density) and the reticular dermis (deeper, dense irregular connective tissue, thick collagen bundles, the bulk of dermal thickness). The papillary-reticular junction is the single most important tissue boundary in body art. Tattoo pigment must reach the papillary to upper reticular dermis for permanence. Too shallow means shedding. Too deep means blowout.
When pigment particles enter the papillary and upper reticular dermis, resident dermal macrophages encounter the particles, recognise them as foreign material too large to digest (professional pigment particles are 50-300 nm in diameter), and engulf them through phagocytosis. The macrophages cannot break the particles down. When those macrophages eventually die over months to years, the particles are released and immediately re-engulfed by new macrophages. This cycle continues indefinitely, which is why tattoos fade so slowly and why fresh tattoos look sharpest while older tattoos soften.
Dermal thickness varies dramatically across the body. At the eyelid, total dermis is 0.5-0.7 mm, requiring minimal needle protrusion. At the upper back, dermis is 3.5-4.0 mm, providing a forgiving depth tolerance. A needle depth that works on the upper back will blow out on the eyelid. A tattoo blowout occurs when pigment is deposited into the hypodermis or deep reticular dermis where collagen bundles are widely spaced. The pigment spreads laterally along loose connective tissue planes, producing a blurred bluish halo. The bluish colour is from the Tyndall effect, the same optical phenomenon that makes veins appear blue through skin. Blowout is permanent; laser removal is the only treatment and results are inconsistent.


