
Piercing Infection vs Irritation: Know the Difference Before You Panic
Key Takeaways:
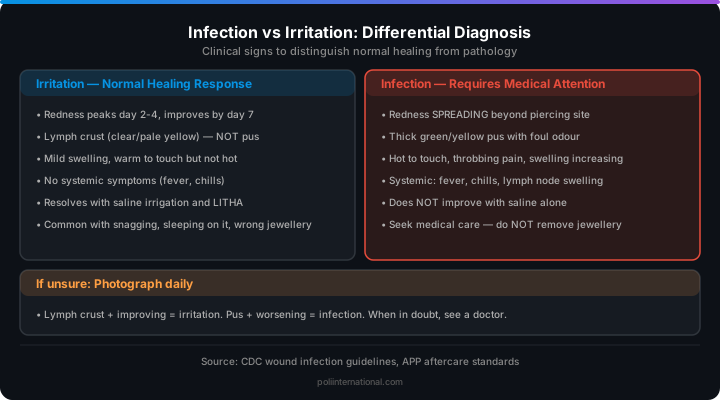
» Normal healing produces redness, swelling, and lymph crust that peaks at days 2-4 and improves by day 7; this is the inflammatory cascade doing its job, not a sign of infection
» Irritation mimics infection with redness and bumps but lacks spreading erythema, purulent discharge, and systemic symptoms; it resolves when the irritant is removed
» The four cardinal signs of a genuine piercing infection are increasing pain, spreading redness, noticeable heat, and thick purulent discharge with a foul odour
» Never remove jewellery from an infected piercing without medical guidance: the channel closes and traps the infection inside the tissue
» Cartilage piercings deserve extra caution; poor blood supply means infections can progress to perichondritis and permanent deformity faster than in soft tissue
1. Normal Piercing Healing: What to Expect
Every new piercing is a controlled injury. The needle creates a channel through tissue, and your body responds with the same inflammatory cascade it uses for any wound. That cascade has recognisable stages that can look alarming if you are not expecting them, which is why every piercer has received a 2 AM message from a client convinced their three-day-old helix is infected when the photo shows a completely normal healing piercing.
During days 1 through 7, the inflammatory phase produces redness within a 2-3 mm radius around the entry and exit points, swelling that peaks at days 2-4 and recedes after day 5, and clear or pale yellow lymph discharge that dries to a whitish crust. This lymph carries immune cells and proteins to the wound; it is not pus. It has no odour or a faint, clean smell. Mild tenderness when the jewellery moves is normal, as is some local warmth from increased blood flow to the area. These symptoms should improve noticeably within 5-7 days. If redness and swelling are still increasing after day 5, something else is happening.
By weeks 2-6, the proliferative phase begins. Lymph crusting decreases. The area may remain slightly pink but swelling should be gone. A small, firm ring of scar tissue called a healing cuff forms around the channel. The piercing feels less tender but is still sensitive to rough handling. Even a well-healed piercing can produce small amounts of lymph crust periodically, especially after sleeping on it, changing jewellery, or during illness. Occasional crust alone, without pain, swelling, heat, or discolouration, is benign; it is simply your body's ongoing maintenance of the fistula.
2. Irritation: The Mimic That Causes Most False Alarms
Irritation looks more dramatic than normal healing but is not an infection. It is your tissue reacting to something it does not like: pressure, friction, chemical exposure, or jewellery material. Common irritants include sleeping on the piercing (producing one-sided redness worse in the morning), jewellery that is too short or tight (ball embedding into skin, persistent redness), harsh cleaning products like alcohol, peroxide, or tea tree oil (dry, flaky skin and stinging), excessive movement or twisting of the jewellery, hair and cosmetic products contacting the site, and nickel-containing jewellery that triggers contact dermatitis.
Irritation bumps are small, flesh-coloured or slightly pink raised areas next to the piercing hole. They are hypertrophic scar tissue and the single most common reason people mistakenly believe they have an infection. Unlike infection, bumps are firm (not fluid-filled), usually painless or only mildly tender, have no heat or spreading redness, and resolve when the source of irritation is removed. For a full differential diagnosis between irritation bumps and keloids, see our piercing bumps vs keloids guide.
3. Infection: The Signs That Mean You Need to Act
A genuine piercing infection is a bacterial colonisation of the wound channel. It is uncommon with proper aftercare but needs prompt attention when it occurs. The infection is localised in most cases; systemic spread is rare but possible with certain piercings or in immunocompromised individuals. The four cardinal signs that distinguish infection from irritation are:
Increasing pain: throbbing, worsening pain that does not match the age of the piercing. A three-week-old piercing should not hurt more than it did at one week. Pain that intensifies rather than subsides is a red flag.
Spreading redness: erythema extending well beyond the immediate piercing site, especially if it forms streaks radiating outward. Redness expanding beyond 1 cm from the site, or that continues to enlarge hour by hour, is concerning and may indicate cellulitis.
Heat and swelling: the area is noticeably hot to the touch compared to surrounding skin, with swelling that is firm, tense, and unresponsive to cold compresses. Unlike the mild warmth of normal healing, infected tissue radiates heat that a partner can feel from an inch away.
Purulent discharge: thick, yellow, green, or grey pus with a foul or sweet odour. This is the most definitive sign. Clear lymph is not pus; if it has no smell and is pale, it is almost certainly lymph. Systemic signs like fever over 38°C, chills, or swollen, tender lymph nodes near the piercing site indicate the infection may be spreading beyond the local wound.
| Symptom | Irritation | Infection |
|---|---|---|
| Redness | Localised, 2-5 mm around site, fades with cause removal | Spreading, may form streaks, does not improve with home care |
| Pain | Tender to touch, stable or improving over time | Throbbing deep pain, worsens day by day |
| Swelling | Mild, fluctuates, responds to cold compress | Firm, tense, unresponsive to cold, may be significant |
| Discharge | Clear or pale yellow lymph, minimal, no odour | Thick yellow/green/grey pus, moderate to heavy, foul odour |
| Heat | Mild local warmth confined to immediate site | Noticeably hot, markedly warmer than surrounding skin |
| Systemic | None | Possible fever, chills, swollen lymph nodes, malaise |
Red flags that require immediate medical attention: red streaks radiating from the piercing site, fever over 38°C with piercing symptoms, swollen tender lymph nodes near the piercing, rapidly spreading redness suggesting cellulitis, a growing or painful abscess, or any of the above with a compromised immune system or diabetes. Cartilage piercings deserve special caution: ear and nose cartilage has poor blood supply. Infections in cartilage can progress to perichondritis (infection of the cartilage sheath) or chondritis (cartilage death), which can cause permanent deformity. Cartilage infections should be seen by a medical professional sooner rather than later.
4. Rejection: The Third Possibility Most People Miss
Infection and irritation are not the only explanations for a piercing that will not settle. The third is rejection: the body treating the jewellery as a foreign object and slowly pushing it back out through the tissue. It is not bacterial, it does not respond to aftercare, and it is the one outcome where waiting makes the result permanently worse.
Rejection announces itself differently from both conditions above. The jewellery moves. Over weeks, the entry and exit points drift closer together as the tissue bridge between them thins. The skin over the bar turns shiny, tight, or translucent, and the outline or colour of the jewellery starts to show through it. The holes enlarge and the jewellery begins to sit loose or hang at an angle. The channel flakes and peels along its length rather than crusting at the openings. What you will not see is pus, fever, spreading redness, or the deep throbbing pain described in section 3. Rejection is usually painless, which is exactly why it gets ignored until the scar is unavoidable.
Surface and shallow piercings reject most often: navel, eyebrow, surface bars, nape, and dermal anchors. Piercings through generous, well-supported tissue reject rarely. The usual causes are a gauge too thin for the site, which cuts through tissue like a cheese wire, the wrong material in a reactive body, placement that fights the anatomy, or repeated trauma from clothing, sleeping, and knocks.
| Sign | Irritation | Infection | Rejection |
|---|---|---|---|
| Onset | Hours to days after a trigger | Days, often after a specific event | Weeks to months, gradual |
| Pain | Tender, stable or improving | Throbbing, worsens day by day | Usually none |
| Discharge | Clear or pale lymph, no odour | Thick yellow/green pus, foul odour | Little to none, dry flaking |
| Jewellery position | Unchanged | Unchanged | Visibly migrating toward the surface |
| Tissue over the bar | Normal thickness | Swollen, hot, tense | Thinning, shiny, sometimes translucent |
| Responds to aftercare | Yes, once the cause is removed | No, needs medical treatment | No, only removal stops it |
The measurement that decides it: check how much tissue still covers the jewellery. Once less than roughly 4 mm remains, or the bar is visible through the skin, the piercing should come out. Removing it early leaves a small flat scar. Letting the body finish the job leaves a split, a long stretched scar, and a site that may never hold a piercing again.
If this is what you are seeing, the full diagnostic walkthrough is in how to know if your piercing is rejecting, and the piercing migration risk tool scores a placement before you commit to it. Where the material is the suspect rather than the placement, titanium versus surgical steel is the comparison that matters.


