
Tattoos, Piercings, and Pregnancy: An Evidence-Based Safety Guide
Key Takeaways:
» Pregnancy induces relative immunosuppression, particularly in the first and third trimesters, lowering the threshold for bacterial infection at any wound site, including tattoos and piercings.
» No controlled human trial has studied tattoo pigment distribution during pregnancy, but nanoparticles from tattoo ink have been documented in lymph nodes, and the systemic distribution during organogenesis is unknown.
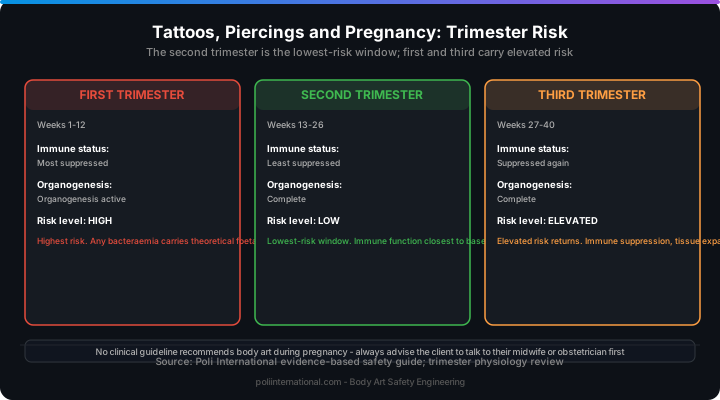
» The second trimester represents the lowest-risk window for body art procedures: organogenesis is complete, the immune system is at its least suppressed, and the uterus is not yet mechanically compressing major vessels.
» Medical consensus across dermatology and obstetrics organisations is cautionary but not absolutist. The risk is elevated, not binary, and individual clinical context matters.
1. Why Pregnancy Changes the Risk Profile
Pregnancy reshapes the immune, circulatory, and dermatological systems in ways that directly affect how any skin procedure heals. The changes are not subtle and the concerns are not hypothetical.
Immune suppression. Pregnancy induces a state of relative immunosuppression to prevent maternal immune rejection of the foetus. This suppression is most pronounced during the first trimester, when the placenta is establishing, and the third trimester, when progesterone levels peak. A lower threshold for bacterial infection at any wound site is the direct consequence.
Bacteraemia risk. A tattoo is an open dermal wound with thousands of micro-punctures. A piercing creates a through-and-through fistula. Both are portals for staphylococci, streptococci, and pseudomonas. If bacteria enter the bloodstream during the first trimester, when organogenesis is most active, the theoretical risk to foetal development is highest.
Pigment distribution unknowns. Tattoo ink pigments are engineered to be insoluble and persistent in the dermis, but nanoparticles from ink have been documented in lymph nodes in multiple histological studies. The long-term systemic distribution of these particles during pregnancy has not been studied in controlled human trials, and it likely never will be, because the ethical barriers to conducting such a study are insurmountable.
Dermatological changes. Pregnancy increases skin elasticity, melanin production (chloasma), and vascularity. These changes are transient and individual. A tattoo applied to hyperpigmented skin may appear different after hormone levels normalise postpartum. A piercing placed in tissue that is more vascular than usual may bleed more and heal unpredictably.
2. Trimester-by-Trimester Risk Assessment
| Trimester | Immune Status | Organogenesis | Recommendation |
|---|---|---|---|
| First (weeks 1-12) | Most suppressed | Active | Highest risk. Any bacteraemia during organogenesis carries theoretical foetal risk. Defer all body art procedures. |
| Second (weeks 13-26) | Least suppressed | Complete | Lowest risk window. Immune function is closest to pre-pregnancy baseline, organ systems are formed, and the uterus has not yet compressed major vessels. |
| Third (weeks 27-40) | Suppressed again | Complete | Elevated risk returns. Immune suppression, mechanical discomfort, and proximity to delivery make body art procedures inadvisable. |
3. Piercing-Specific Considerations
Existing piercings. Most well-healed piercings require no intervention during pregnancy. The jewellery can remain in place unless the piercing site becomes irritated by tissue expansion, which is most common with navel piercings in the third trimester. Flexible, biocompatible retainers made from medical-grade polymer (PTFE or BioFlex) can replace metal jewellery if needed.
New piercings. The healing timeline for a new piercing is 6-12 months for cartilage and 4-8 weeks for soft tissue. Starting a healing process during pregnancy means navigating the entire inflammatory phase under altered immune function. The navel piercing is the worst choice during pregnancy: the expanding abdominal wall places mechanical stress on the fistula, and the stretching skin changes the angle of the piercing, increasing the risk of migration and rejection.
Nipple piercings and breastfeeding. Nipple piercings that have fully healed and formed a stable fistula can usually remain in place during breastfeeding, but the jewellery must be removed before each feed to prevent choking risk. Piercings performed during pregnancy will not be healed by the time lactation begins, and the open wound introduces infection risk to both mother and infant. Most lactation consultants recommend removing nipple jewellery entirely during the breastfeeding period.
4. Tattoo-Specific Considerations
Ink and the developing foetus. The concern is not that pigment particles cross the placental barrier directly, but that the inflammatory response to a fresh tattoo triggers cytokine release and oxidative stress that may affect the foetal environment. No study has quantified this risk, which is precisely why the precautionary principle applies.
Pain management. Topical anaesthetics containing lidocaine are Category B in pregnancy, meaning animal studies have not shown foetal risk, but no controlled human studies exist. The absorbed dose from topical application to a small tattoo area is low, but the absence of data means many clinicians advise against it.
Positioning. After the second trimester, lying flat on a tattoo chair for extended periods can compress the inferior vena cava, reducing venous return and causing supine hypotensive syndrome. Any tattoo session during the third trimester must allow the client to sit or lie on their side.


